Built around ongoing care.
See how ILAI connects the daily record to the next clinical review. Each story is one patient’s record: what ILAI read in it, what it proposed, and what the clinician decided. The patients are synthetic.
Choose a workflow
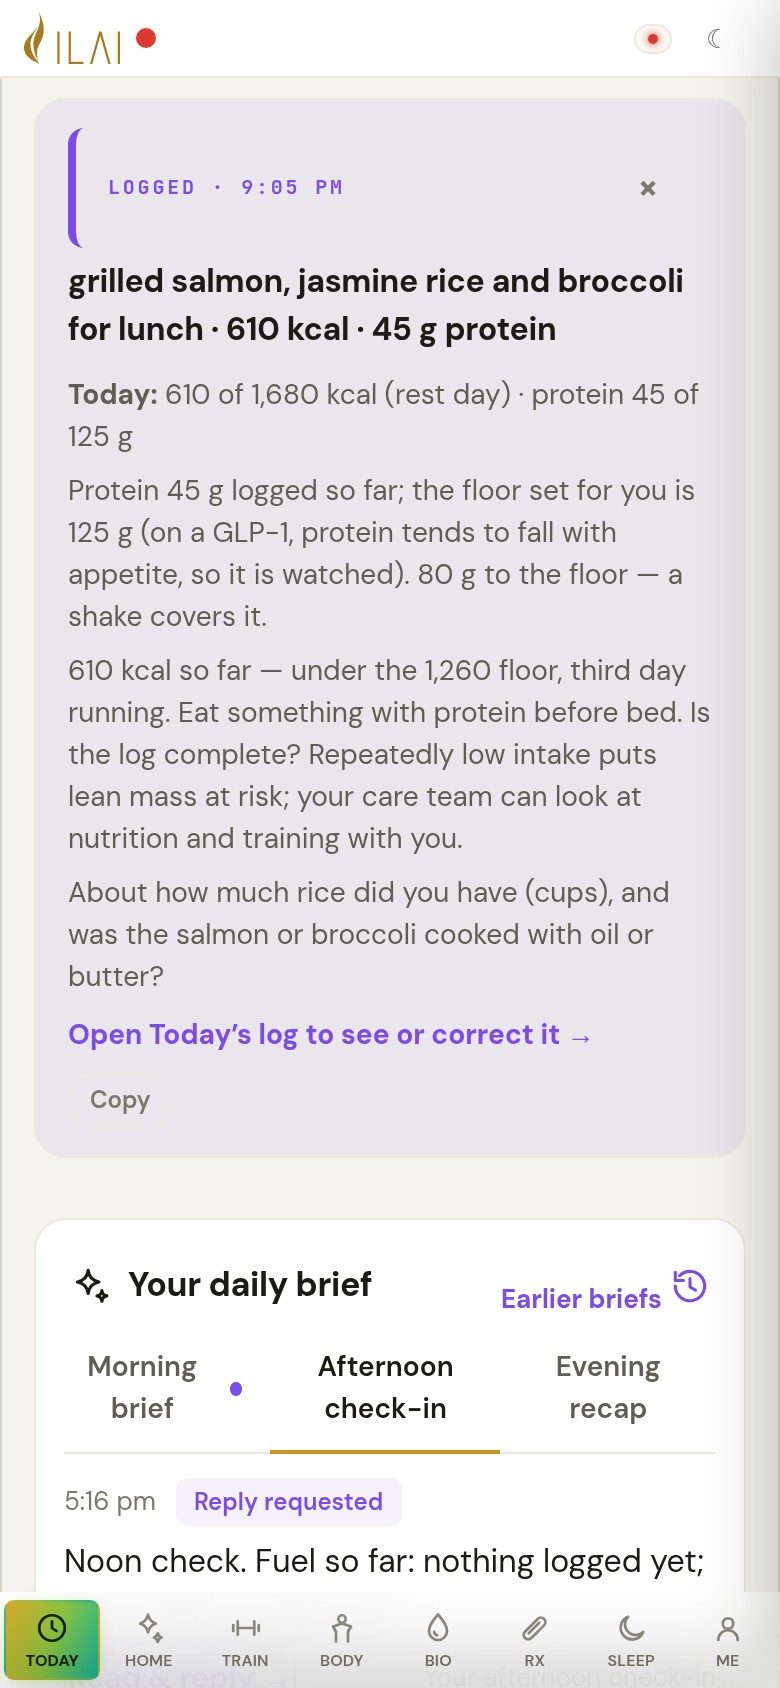
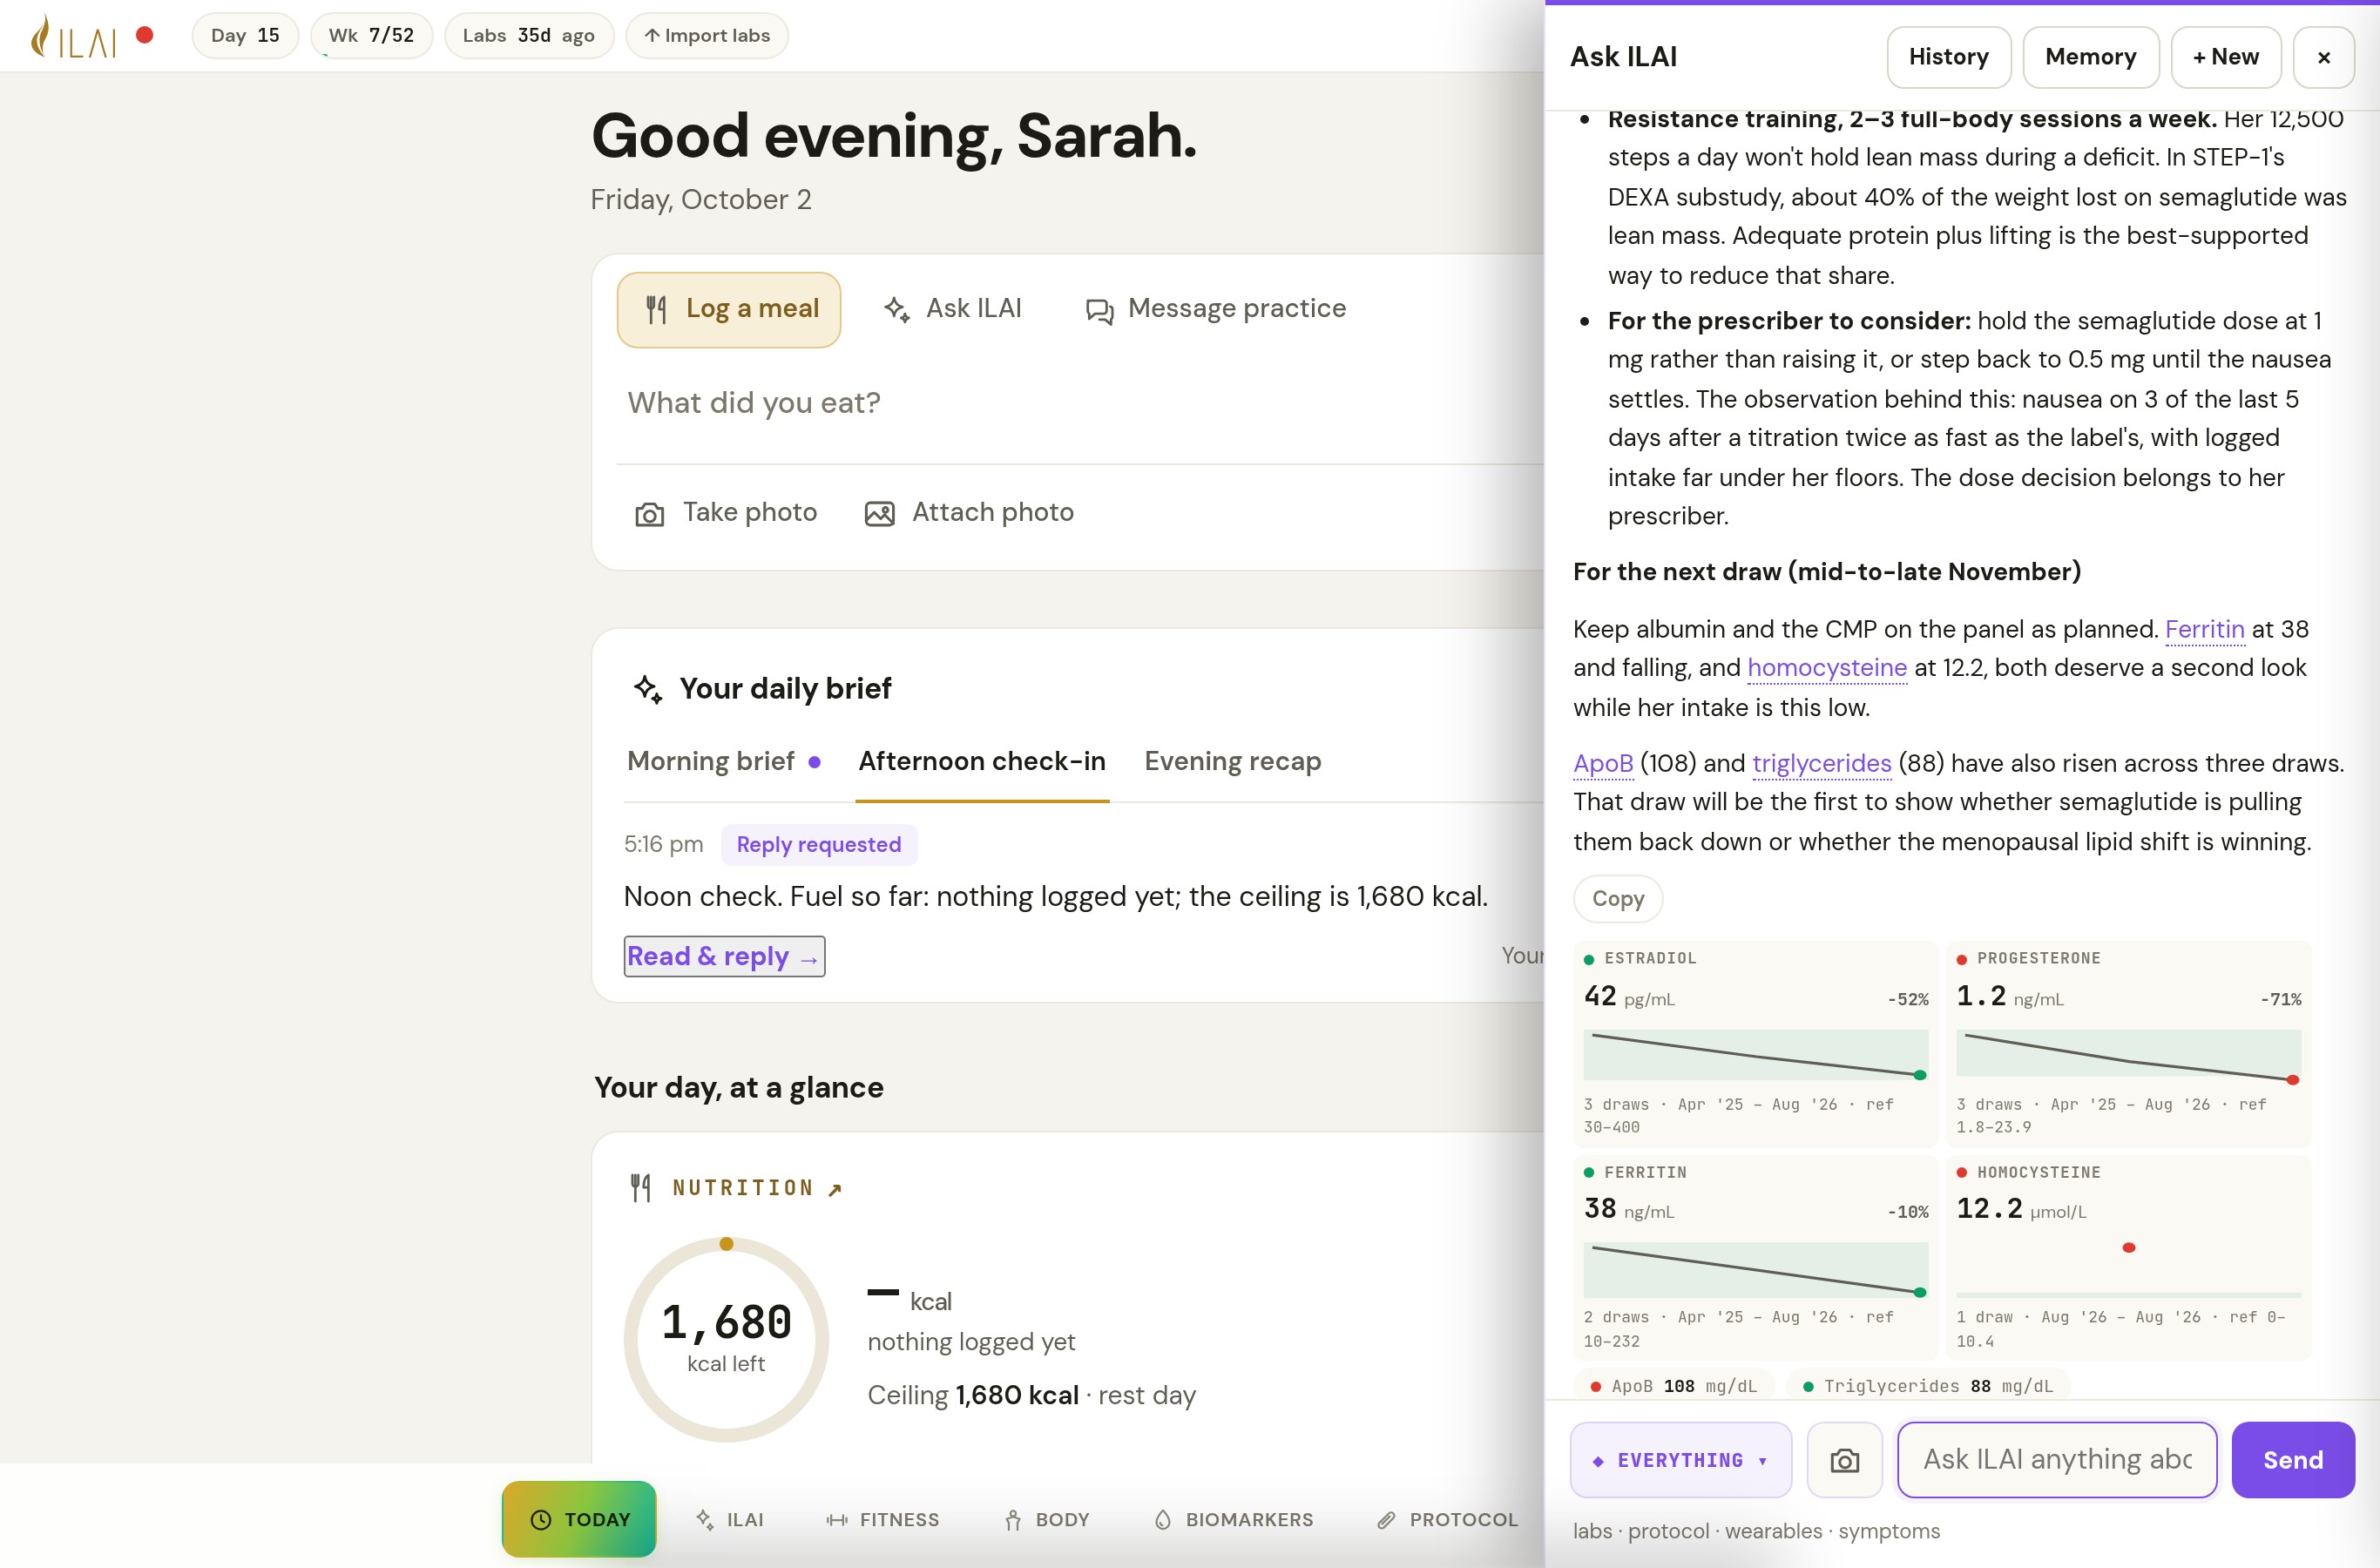
On a GLP-1, ILAI flags low logged intake and asks about the nausea.
Sarah, 45, takes semaglutide and hormone therapy. She sends each meal to ILAI by text or photo so it has the facts. ILAI sets the foods and portions against the floors set for her, beside her weight, symptoms and activity, and asks whether the log is complete before judging low logged intake. When nausea repeats in her log, ILAI asks whether it has affected how much she can drink and raises a possible hydration concern for her care team, in the evening message and on Monday’s practice card, not as real-time monitoring. On her own with ILAI for iPhone, she gets the same read against ILAI’s default floors.
- Meals by text or photoso ILAI has the facts; a wrong read is corrected from the meal’s entry
- Targets set for herILAI’s defaults until her care team sets their own, and every screen says whose number it is
- ILAI at noon and in the eveningwhat the day still needs, whether the log is complete, and the hydration concern when nausea repeats
- The practice sees the numbersunder-floor days and GI symptoms on the clinician card and the weekly report; meal photos are visible only to the patient
Three draws, one direction. ILAI names the pattern.
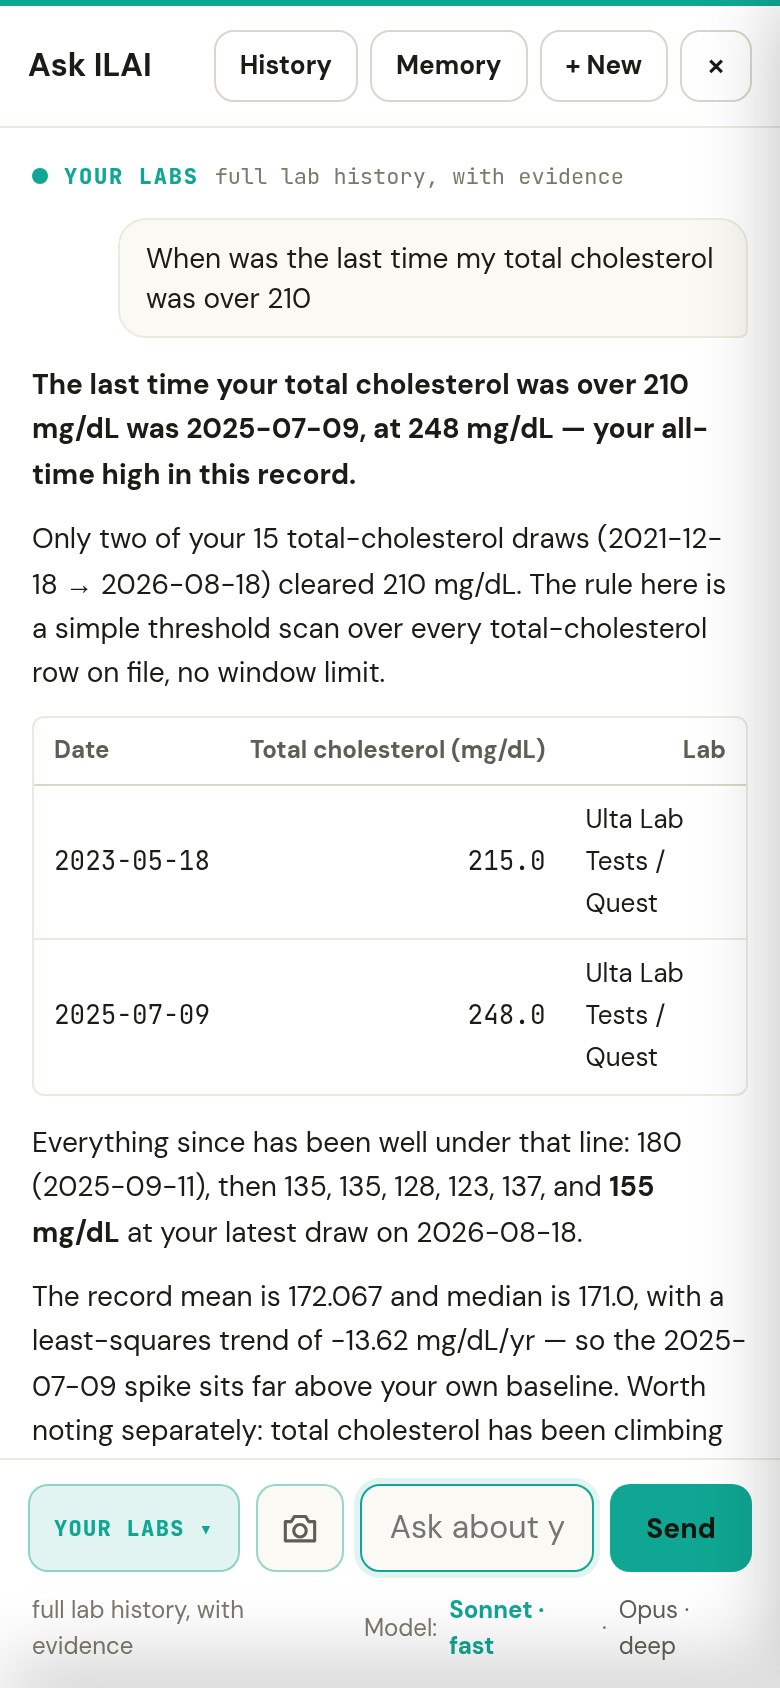
Michael, 43, has no active protocol. ILAI lines up his last three draws: ApoB, ALT, HbA1c and hs-CRP above target three times in a row, each still rising. It puts him under Needs you on Monday’s clinician page, adds Lp(a) to the draft requisition with the rule behind it, and names a coronary calcium scan to schedule. His clinician decides what is ordered.
- ApoB, lipids and Lp(a)against targets your practice sets
- HbA1c, glucose and insulinwith HOMA-IR derived when fasting pairs exist
- Liver and inflammationALT, AST, GGT and hs-CRP, with the rule that fired
- What's missing gets addedLp(a) on the next requisition, a coronary calcium (CAC) scan to schedule
- GLP-1 and peptide protocolsdose ranges and titration in the cycle builder
The cuff, the dose, and what changed.
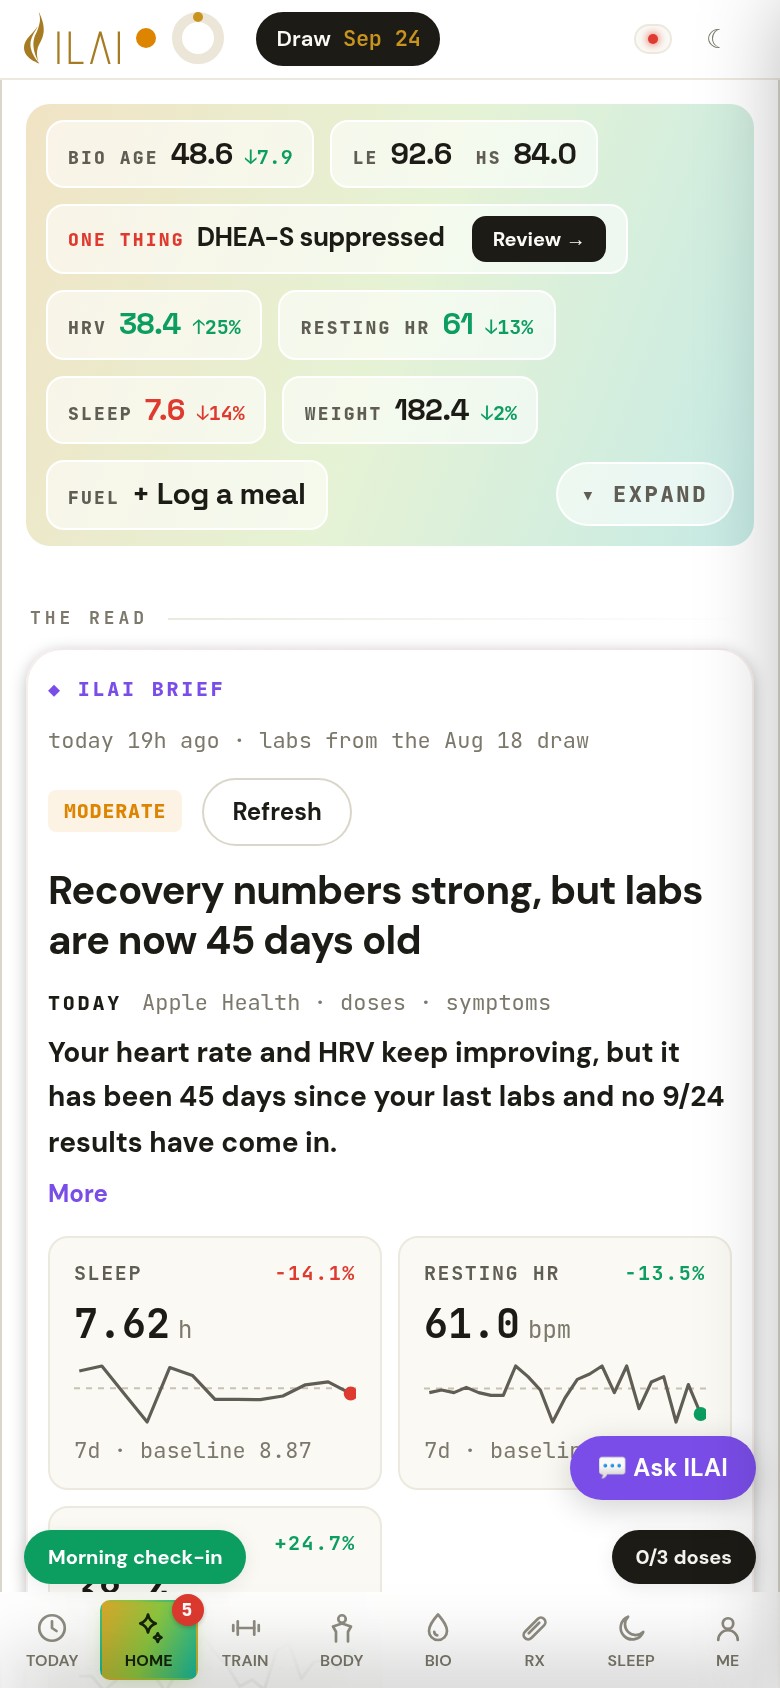
Alex’s morning cuff comes through Apple Health. ILAI compares the 7-day and 30-day means with the target his practice set, marks every dose change of a blood-pressure medicine on the trend, and says what the two weeks before and after looked like. On his record: telmisartan 40 to 80 mg on Aug 30; the two weeks before 129/81, the two weeks after 115/75.
- Means against the practice’s target7 and 30 days, from the cuff, with the number of readings
- Every dose change on the chartwith the two weeks before and after it
- The safety gatea recorded systolic reading at 180 or above is flagged for review; these checks depend on the data available and are not emergency monitoring
- On the clinician card and the Monday reportone line per patient, in plain words
One marker, two labs, one honest trend.
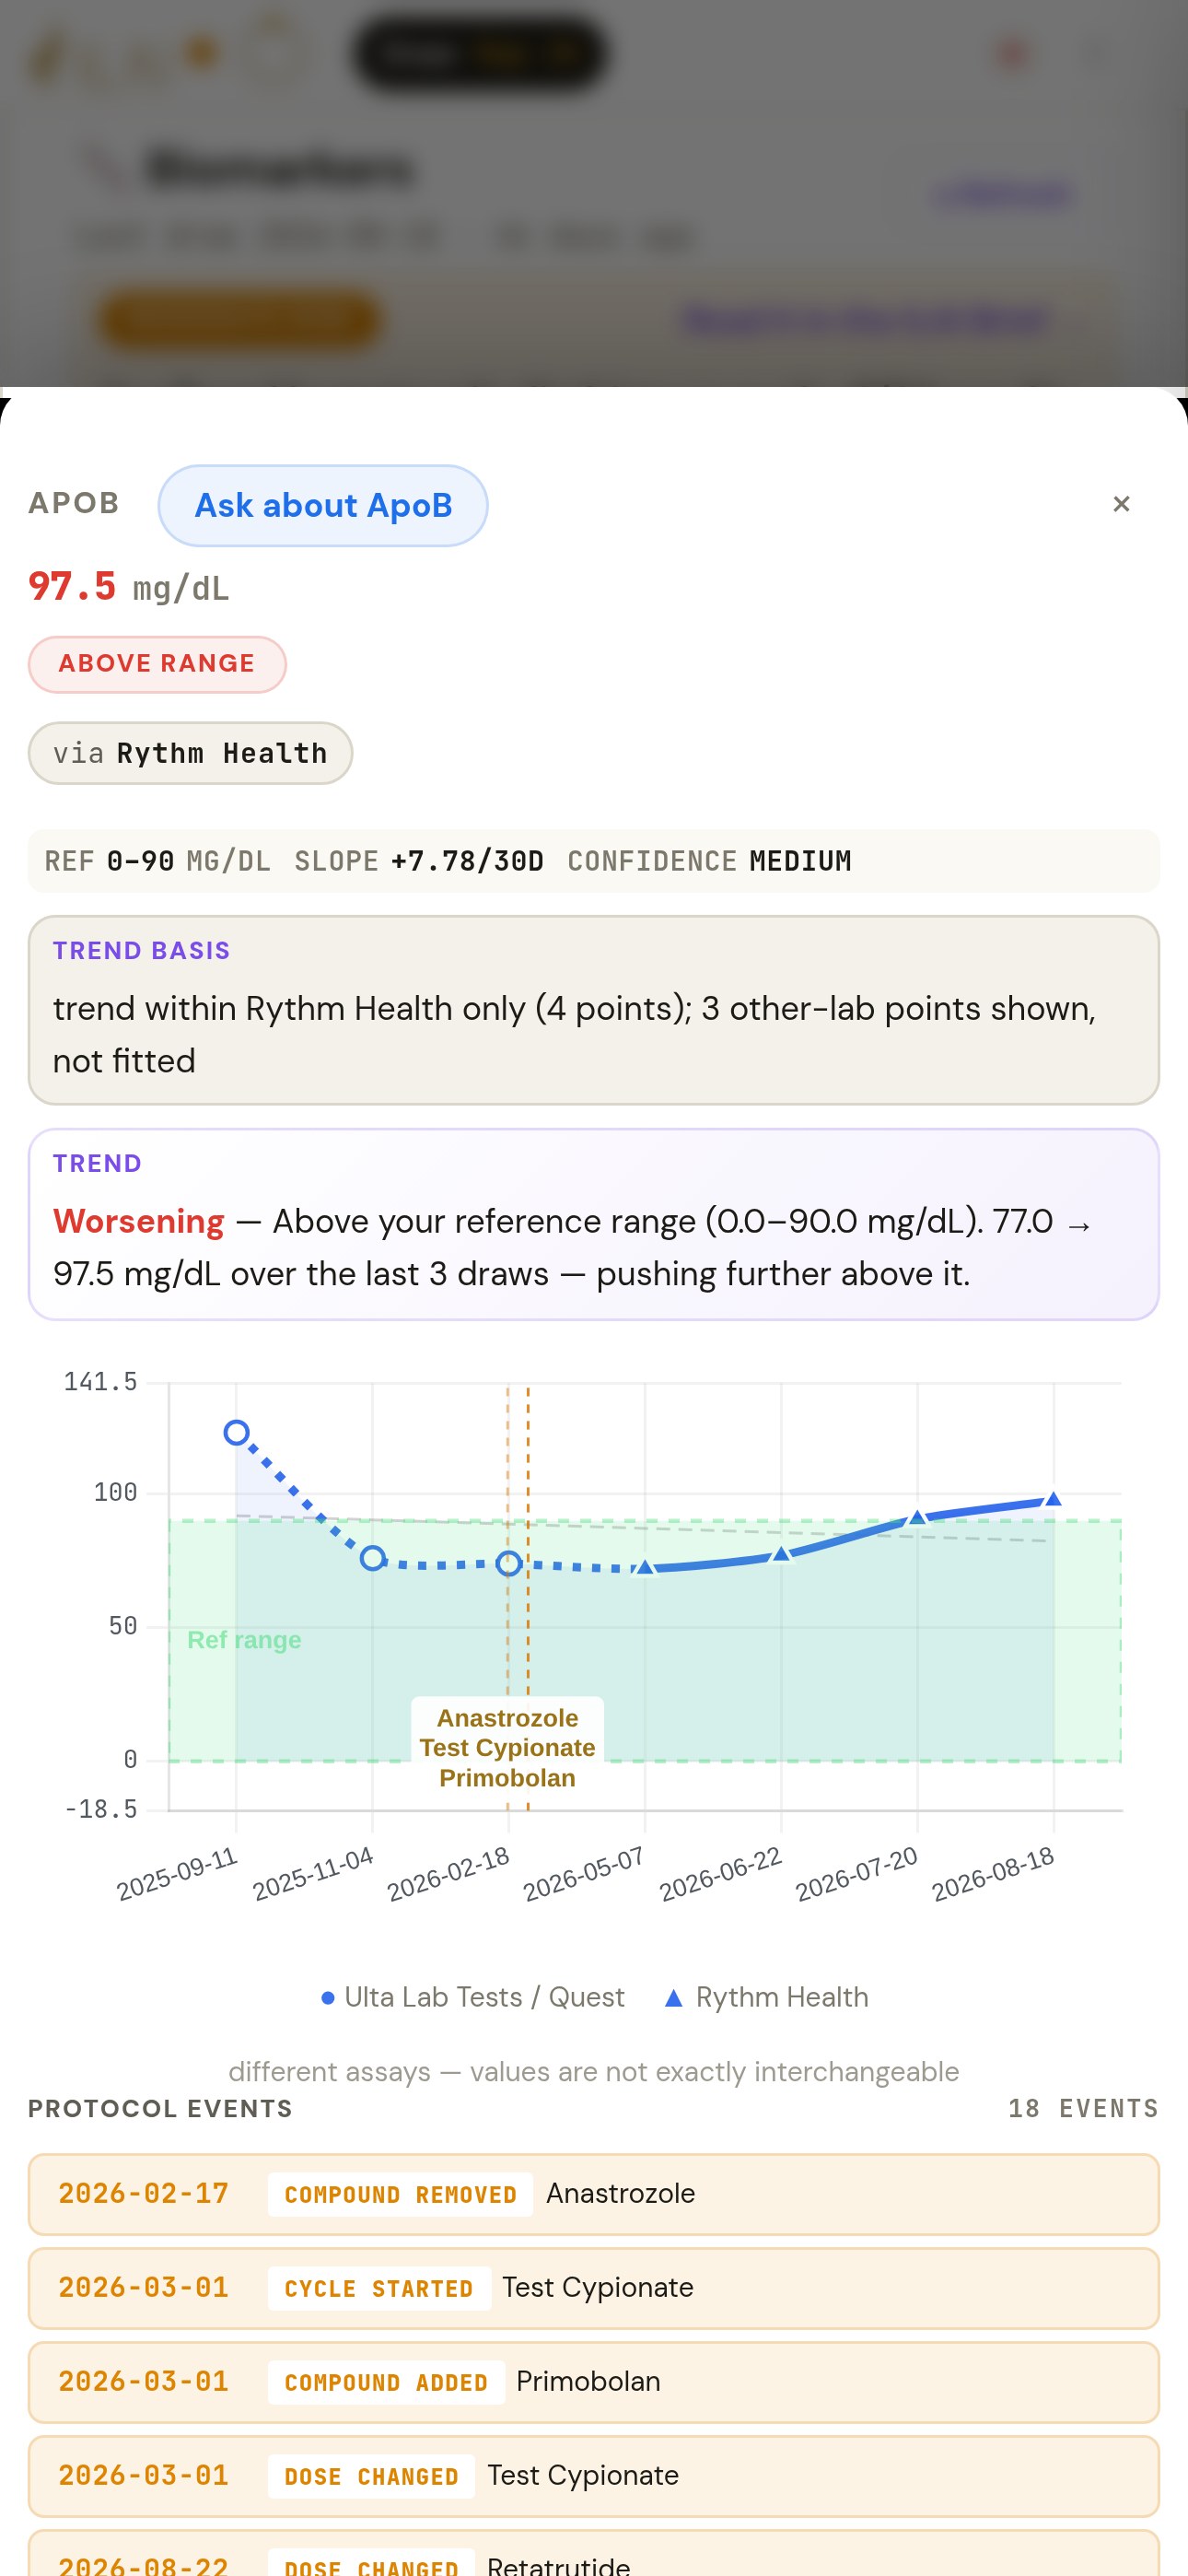
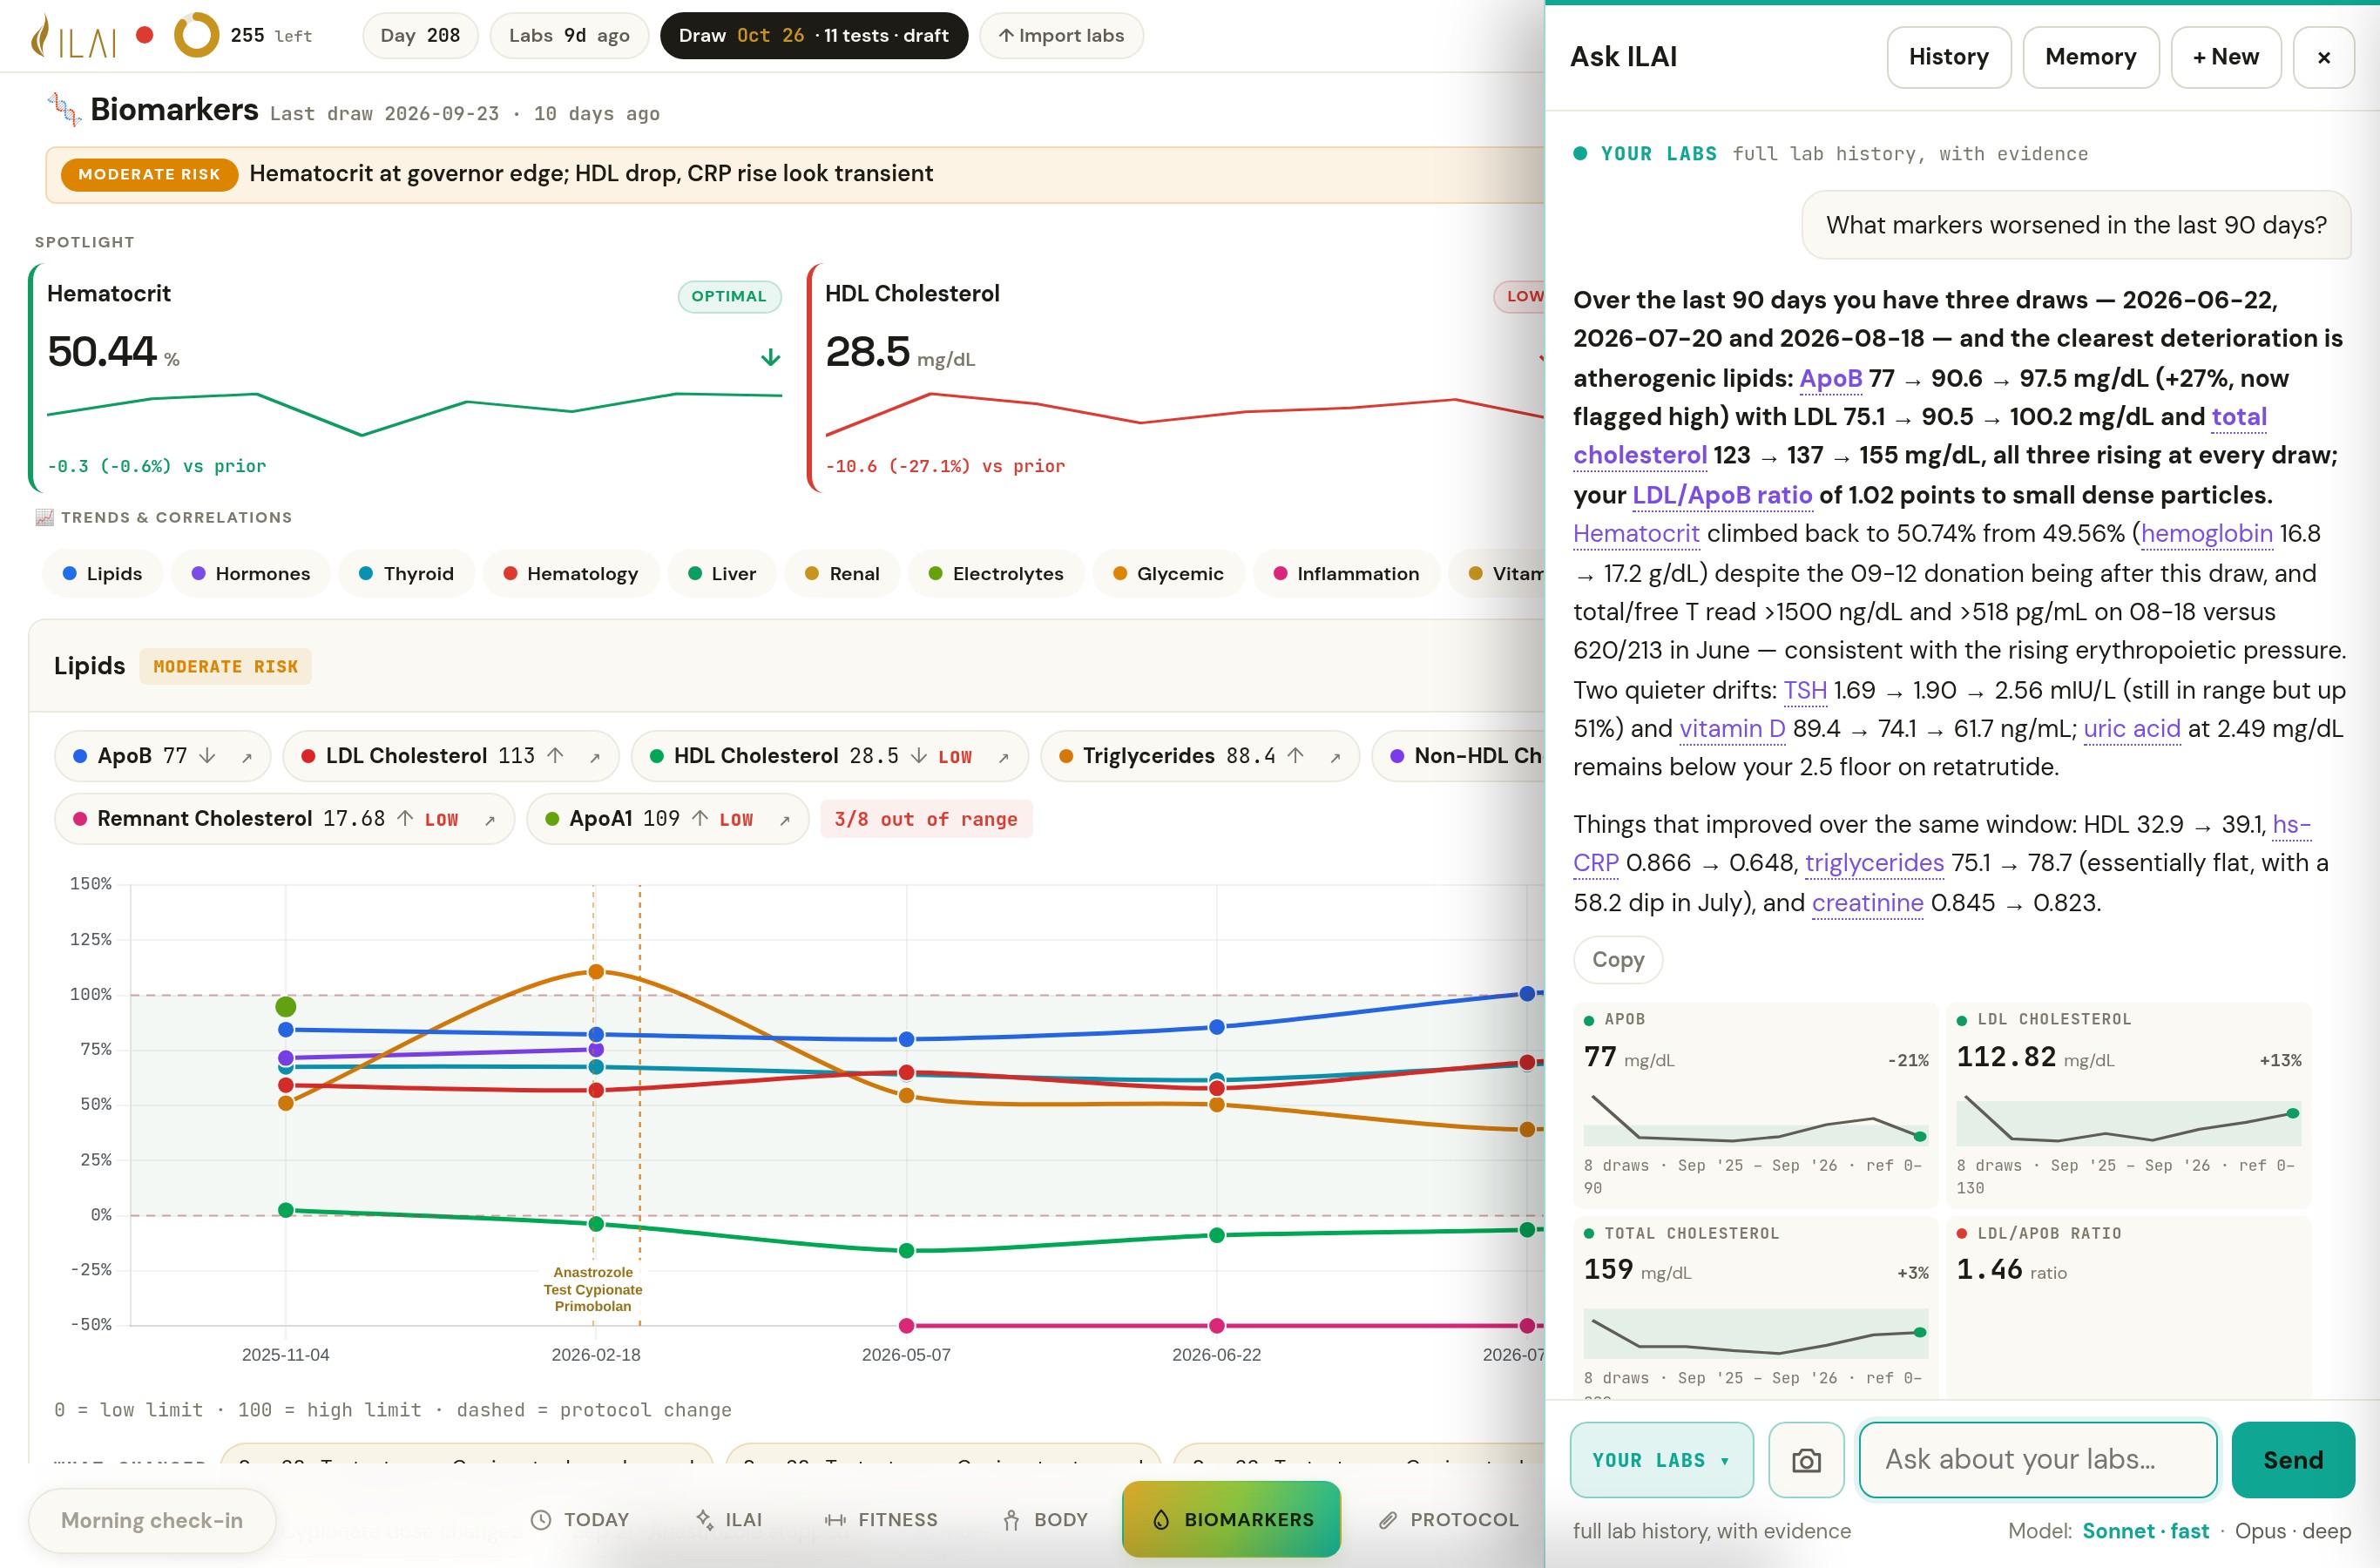
Alex draws at Quest through Ulta Lab Tests and at home with Rythm Health. ILAI fits the trend within one lab and shows the other lab’s points beside it, unfitted, because the assays differ. The last three Rythm draws take ApoB from 77 to 97.5 mg/dL, above range, and the next requisition is where it gets confirmed. The same honest trend holds for anyone who imports their own reports into ILAI for iPhone.
- Trend basis, statedwhich points were fitted and which were only shown
- Different assays, never mixed“values are not exactly interchangeable”, in the legend
- Protocol events on the chartanastrozole, testosterone and Primobolan at their dates
- The clinical lab weighs moreILAI’s PhenoAge weights each input by its lab and method; a primary lab result counts more than an at-home one
TRT and HRT: every result read against the band and the dose.
Alex follows a supervised testosterone protocol. ILAI judges each hormone result against the band set for him and the protocol changes between draws, marks every checkpoint rule evaluated or not at each draw, and, when a result calls for it, proposes the dose change with the calculation. A clinician or practice-admin account accepts or declines; nothing is applied until then.
- Targets with a reasonfree T, hematocrit and estradiol bands, each noting who set it and why
- Cycles with checkpointseach rule marked evaluated or not evaluated at every draw
- Dose changes proposedcomputed from the labs; a clinician or practice admin accepts or declines
- Assay limits respecteda result beyond the assay's reporting limit is kept as a limited value (greater-than or less-than), not as a number
A ceiling, a tier, and the draw that decides.
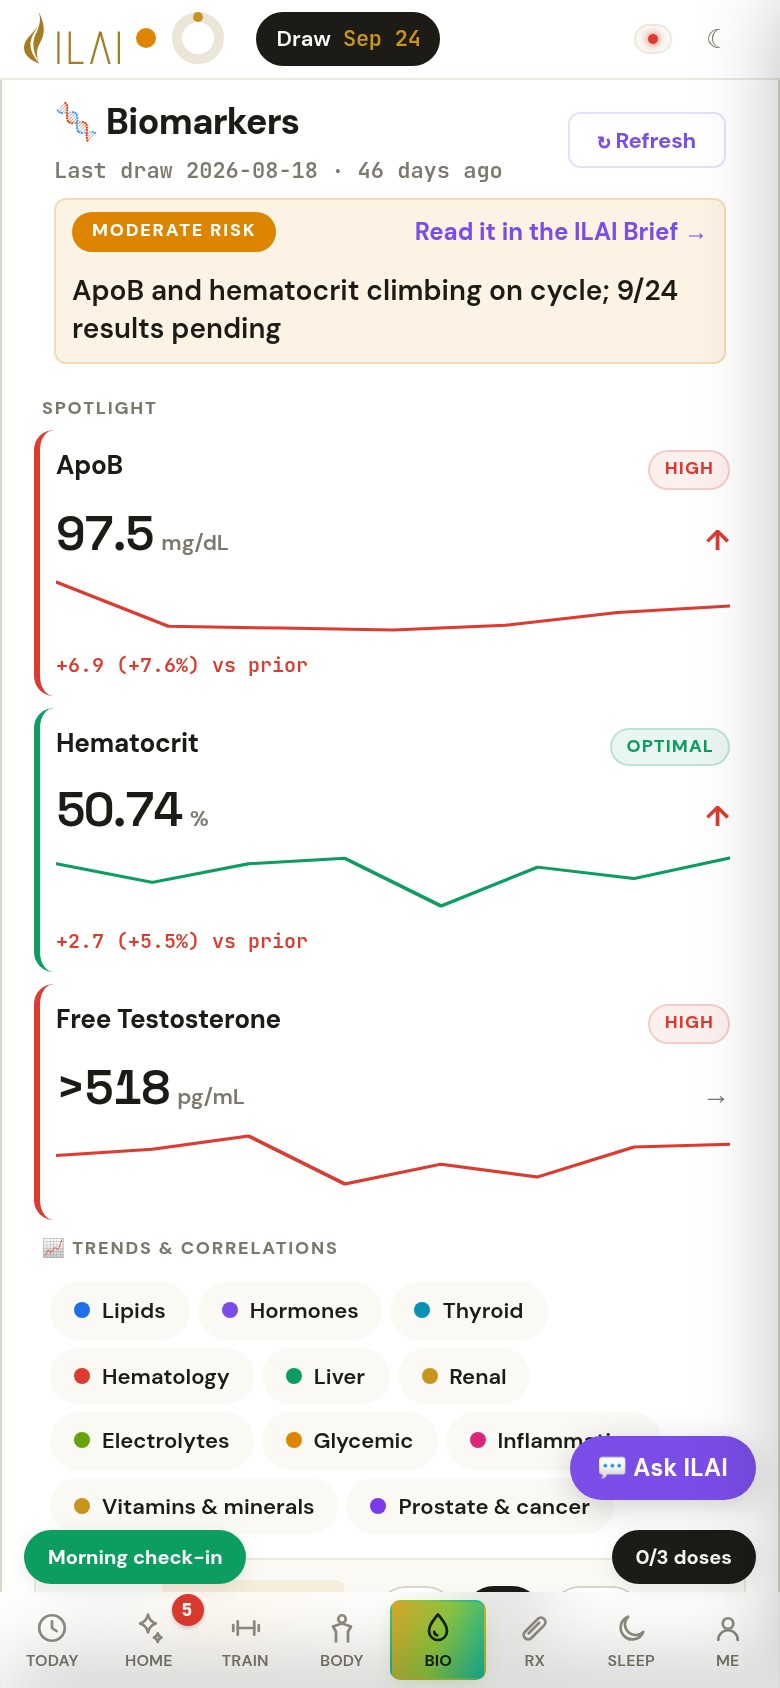
Testosterone raises hematocrit. ILAI sets each result against the ceiling set for the patient (52 unless the care team sets another), places it in a tier, and says what the tier asks for. A blood donation logged after the draw is shown on the timeline; the current hematocrit stays unconfirmed until it is measured again. The 54 gate follows the Endocrine Society 2018 guideline (pause testosterone above 54 until it falls), and the tier reads exactly that — never “keep the dose”. The 52 ceiling and the watch tier from 50 are a practice default, not clinically validated; the care team can set the ceiling per patient, and the sheet says whose number it is and where each tier comes from. Alex’s record: 50.7% on Aug 18, up from 48.1; donated Sep 12, after that draw; testosterone cypionate 43 mg a day; the week-12 draw overdue.
- Four tiers, one ceilingclear · recheck in 4–6 weeks · phlebotomy within 2 weeks and no testosterone increase · at 54, pause testosterone until the clinician reviews
- Donations on the recordlogged from the marker sheet; a donation after the draw leaves the value unconfirmed until the next one
- The next draw, countedthe checkpoint that resolves it, with days to go or days overdue
- Proposed, not appliedat the ceiling the sheet, the clinician card and the Monday report carry the proposal; a clinician or practice-admin account accepts, and nothing is applied until then
Built from a template. Reviewed before it continues.
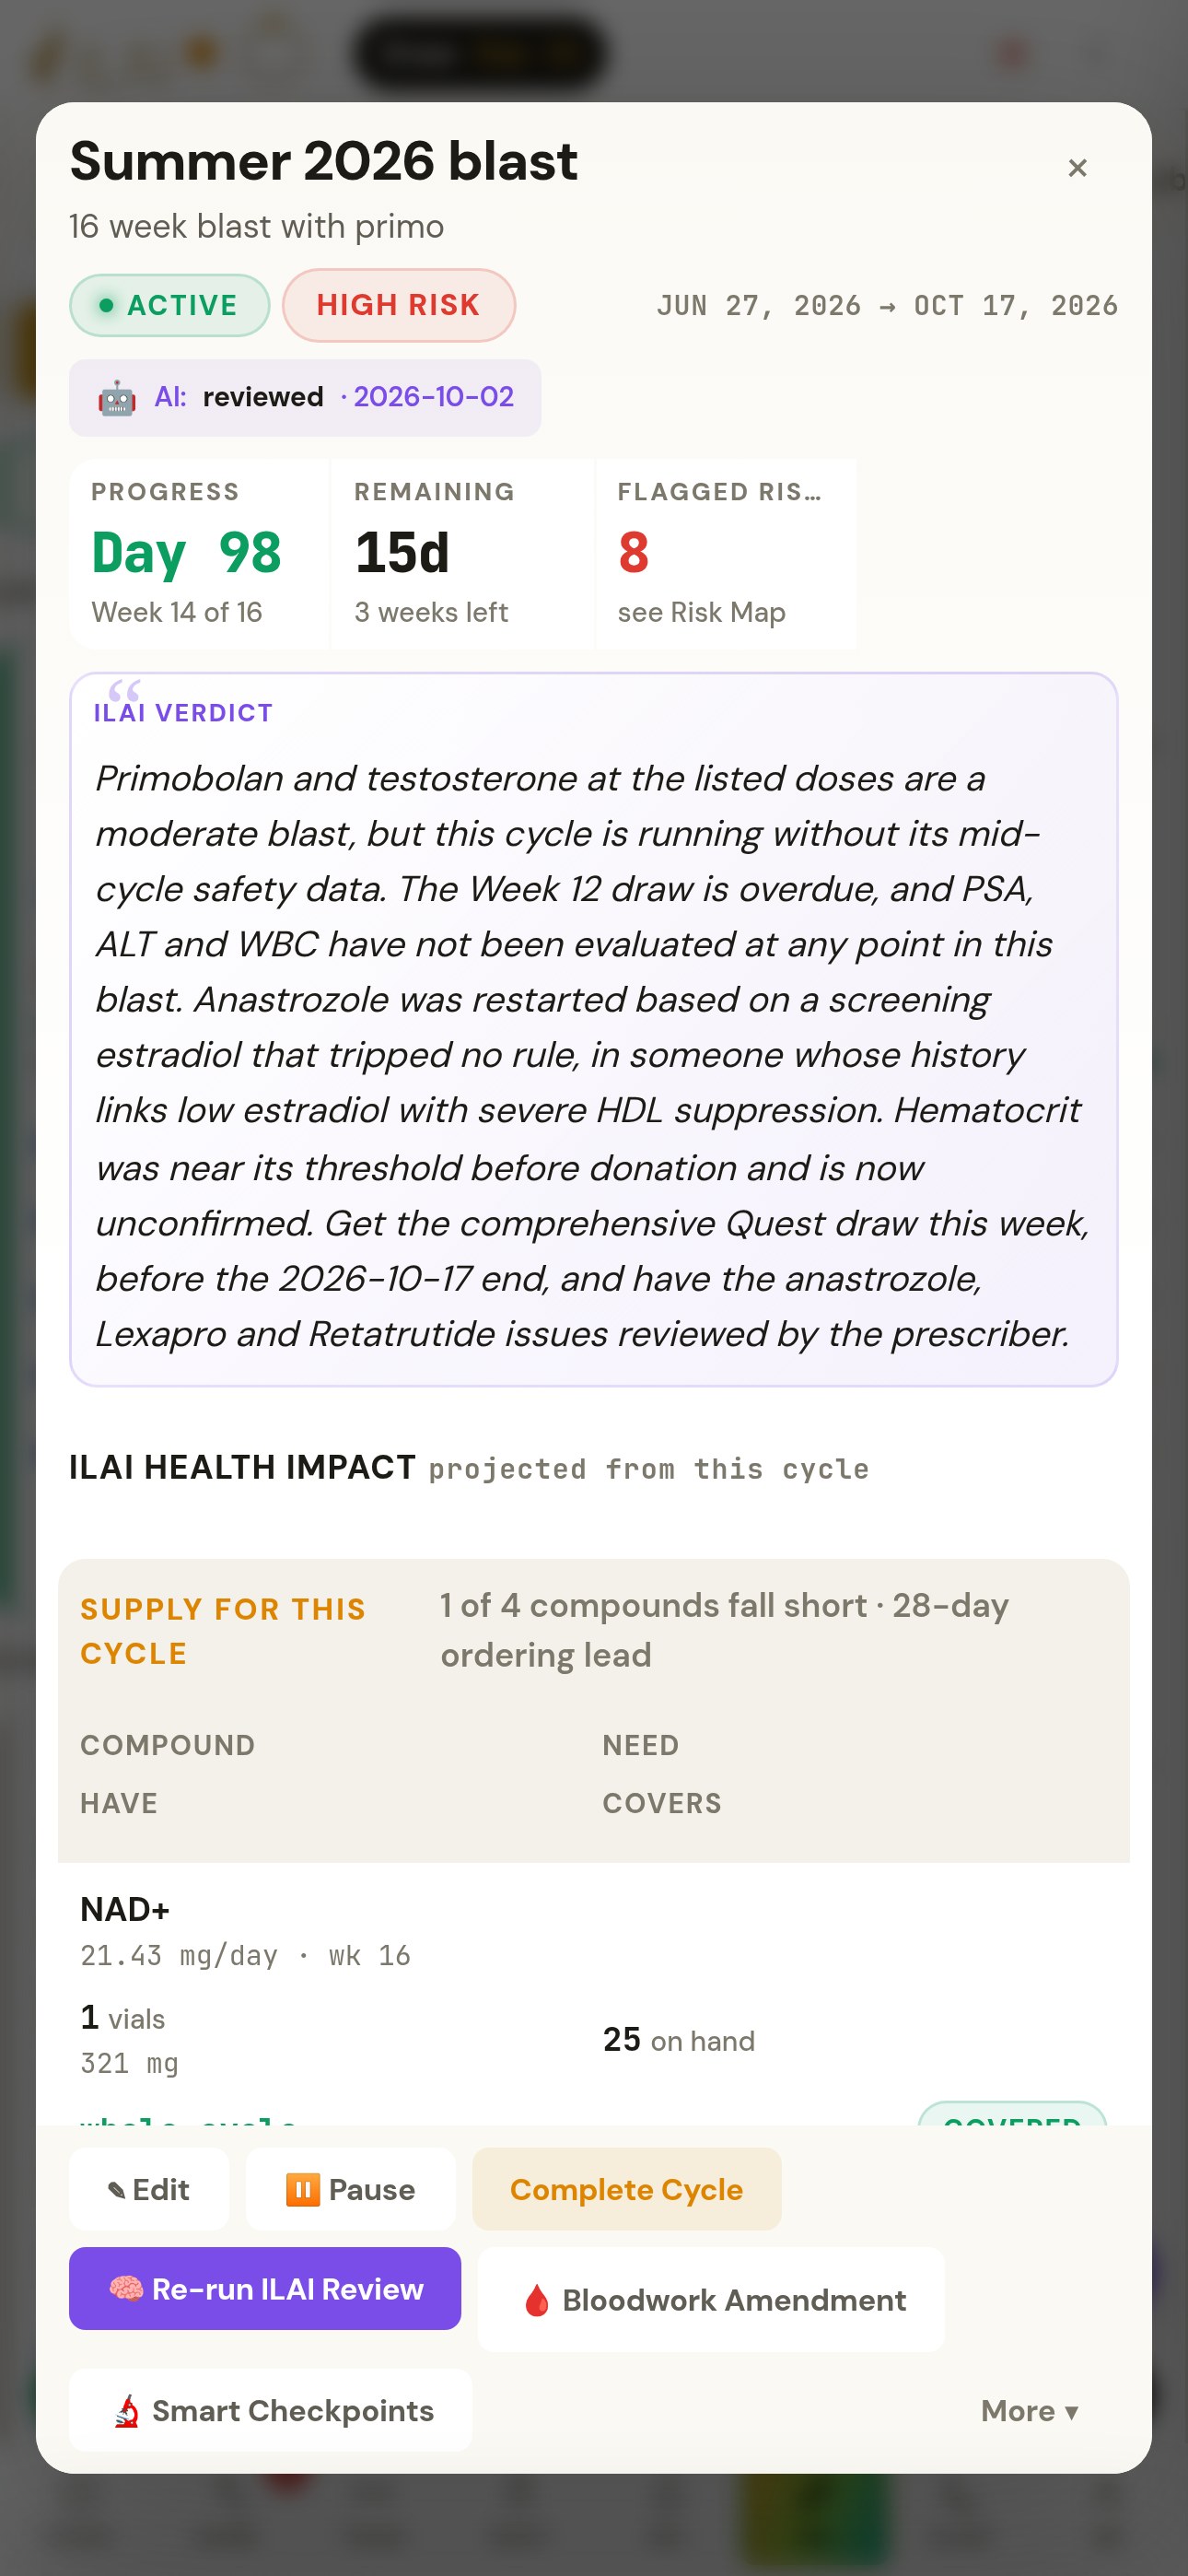
Alex’s 16-week blast (a high-dose cycle) carries five compounds and five checkpoints. ILAI’s review names what it found: no labs since Aug 18, the week-12 draw not yet done, hematocrit just under its 51% threshold, ApoB rising, anastrozole restarted on an estradiol result from a screening method rather than LC/MS. Its verdict: the cycle can finish as planned if the week-12 Quest draw happens and estradiol is confirmed by LC/MS first.
- Checkpoints with rulesthe draw date, the marker each rule watches, evaluated or not
- Supply for the cycleneed, have, how far it covers, against a 28-day ordering lead
- A verdict derived from its own flagsapproval follows the risk flags it raised, shown as the verdict basis
- Accepted by an authorized practice accountnothing is applied until acceptance is recorded, with which account and when. Which accounts are authorized is the practice’s own setting; ILAI checks the account role, and prescribing responsibility remains with the treating clinician
Her results, in the context of her life stage.
Sarah, 45, is in perimenopause. ILAI judges her hormone panel against her menopause status, not a generic range: FSH from 8.2 to 32.8 mIU/mL over three draws while progesterone fell from 8.5 to 1.2 ng/mL, the patch and the progesterone start marked on the chart. It says where that places her and what is still uncertain. Nothing on her protocol changes until a clinician or practice-admin account accepts it.
- Menopause status on recordpre, peri or post; estradiol read against it
- Her hormones chart togetherevery protocol change marked
- Her symptoms counthot flashes, night sweats, libido
- Her body map and reference rangesfemale body map, sex-specific cutoffs
- Her protocolhormone therapy with checkpoints and review
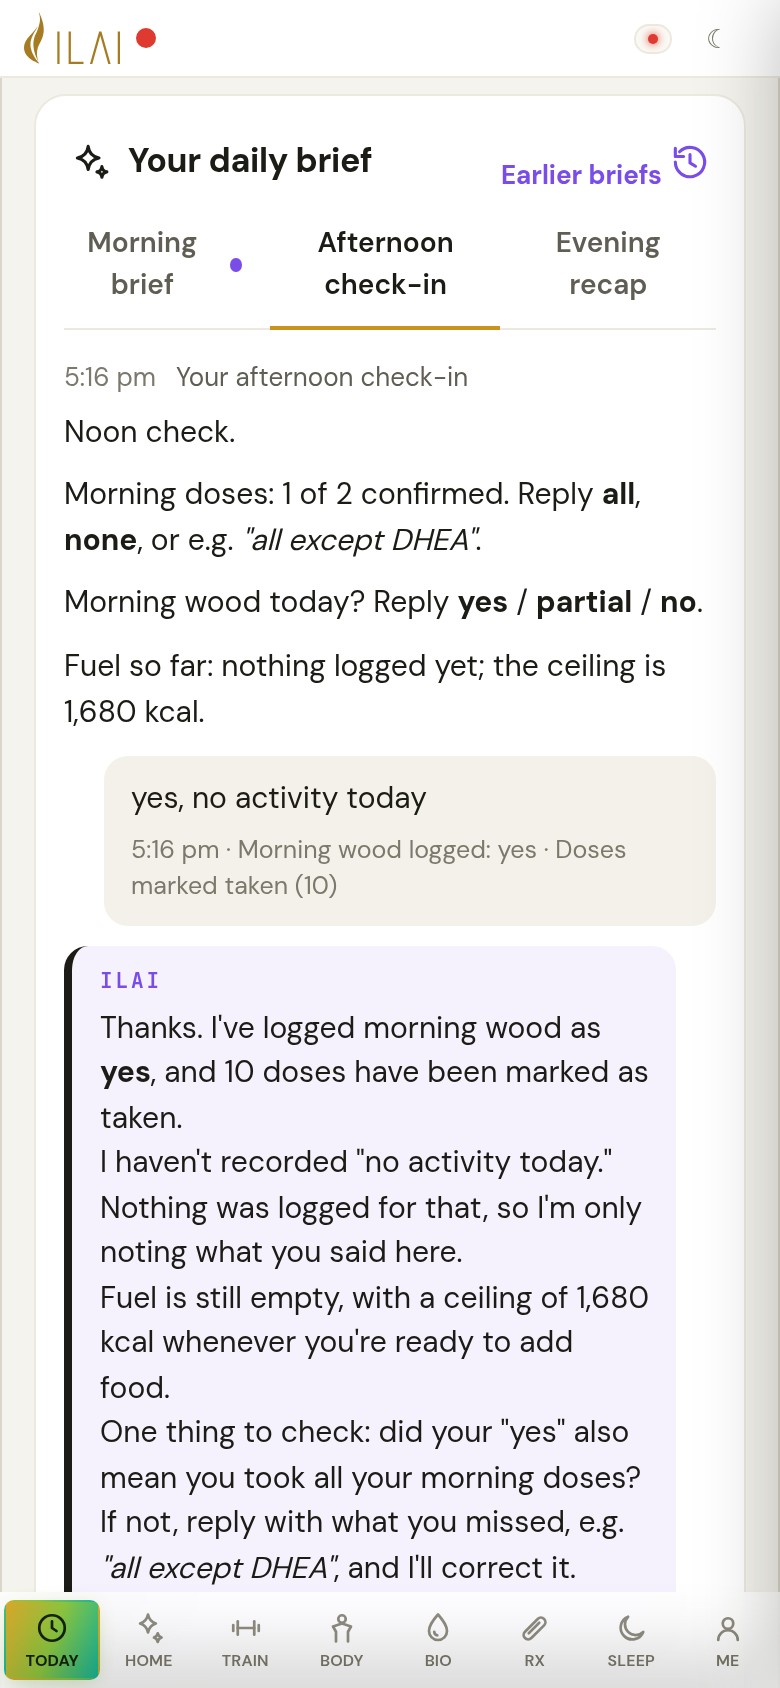
A vital sign most records never collect.
Morning erections are a daily read on vascular and hormonal health that no draw gives you. If it hasn’t been logged in ILAI by midday, ILAI asks on Today, then puts the answer beside the labs. It works the same for someone using ILAI for iPhone on their own.
- One question a day, only if not loggedyes, partial or no
- A rate over timeagainst the prior period
- Correlated with the protocoldoses, labs and wearables
- Seen by the practicewhat the patient logs can appear in the daily brief and on the clinician card, visible to the patient and their authorized care team
- Privatethe daily prompt goes to the patient only; what is logged is in the record and can appear in the daily brief and the clinician card. Entries are visible to the patient and their authorized care team; service providers process data as described on the Security page
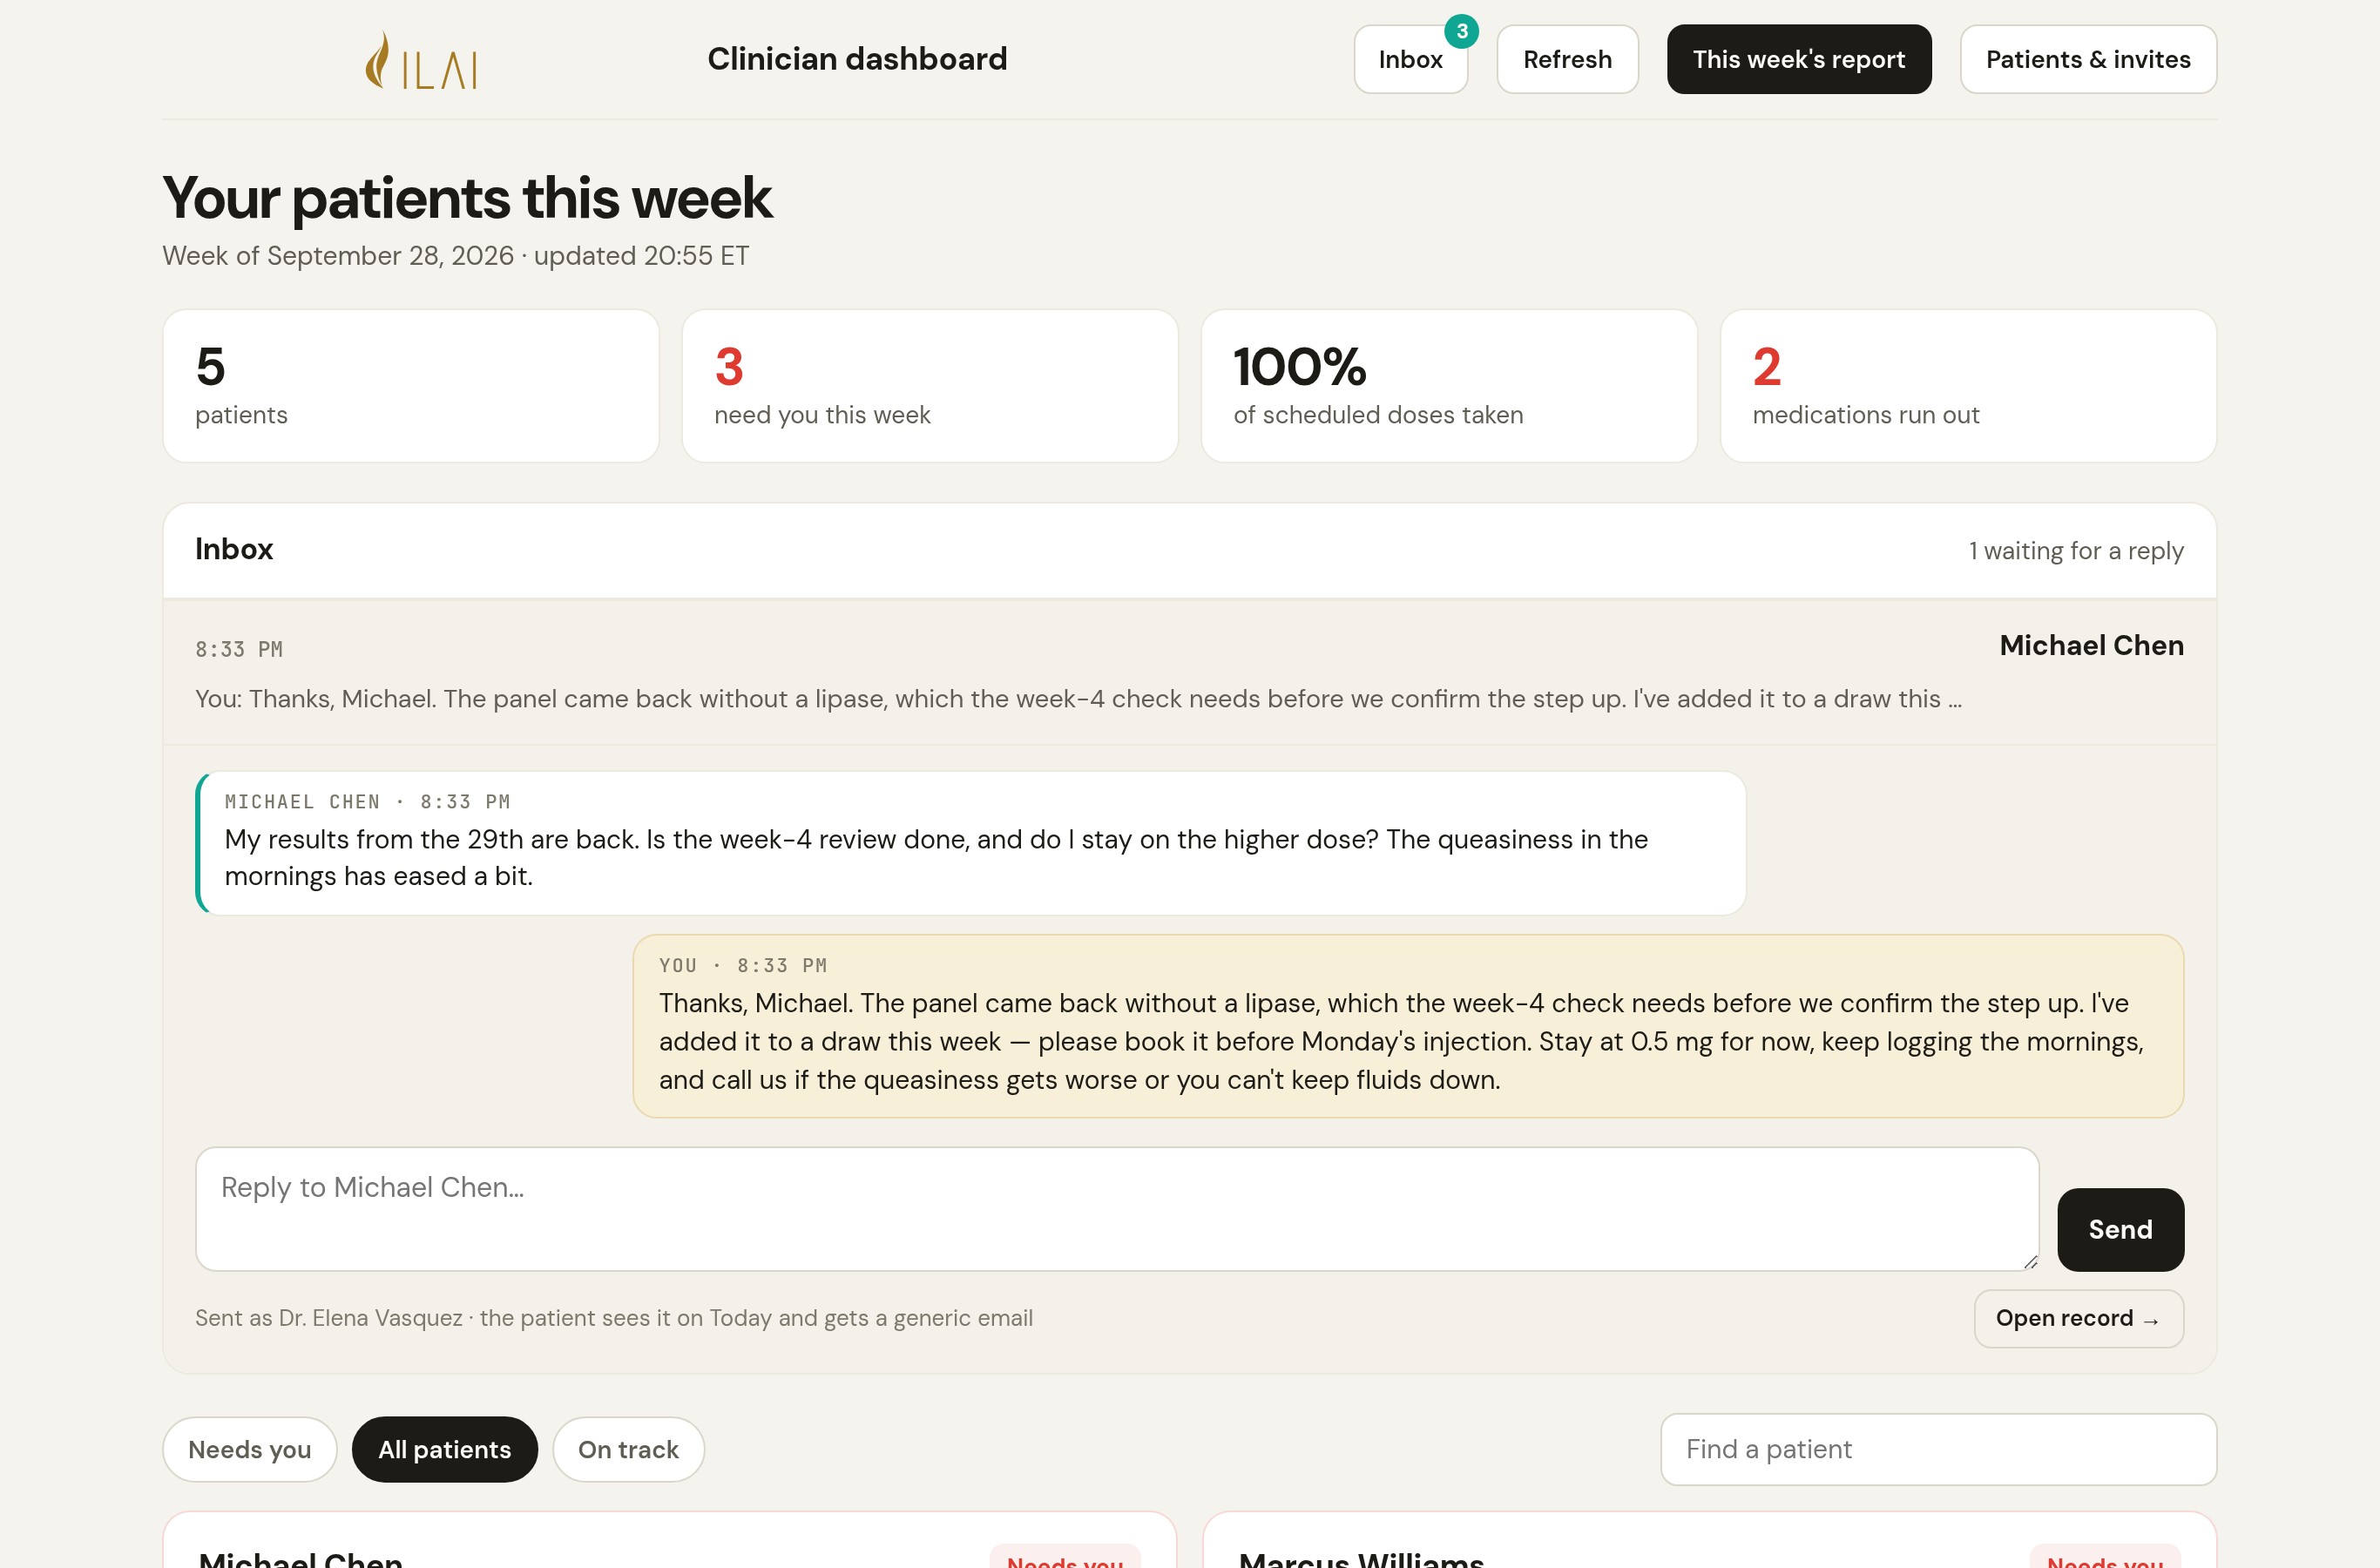
A question between visits
Patients message the practice from Today. Replies appear there and remain available in the conversation. A member writes from the same box that logs a meal or asks ILAI; the practice answers from the clinic page’s Inbox, and the reply appears on Today with the clinician’s name. Unread replies badge the Today tab. The alert email says only “You have a new message in ILAI. Sign in to read it.”
- One box, from Todaythe badge on the composer says whether a line goes to a meal, to ILAI or to the practice; the practice mode says who answers and that it is not for emergencies
- Answered from the clinic page’s Inboxevery patient conversation, unread first, waiting-for-reply flagged, opened in place with the record beside it
- The reply, in the patient’s conversationon Today, with the clinician’s name, and it stays there
- Alerts without contentthe email carries no name and no excerpt; the message is read inside ILAI
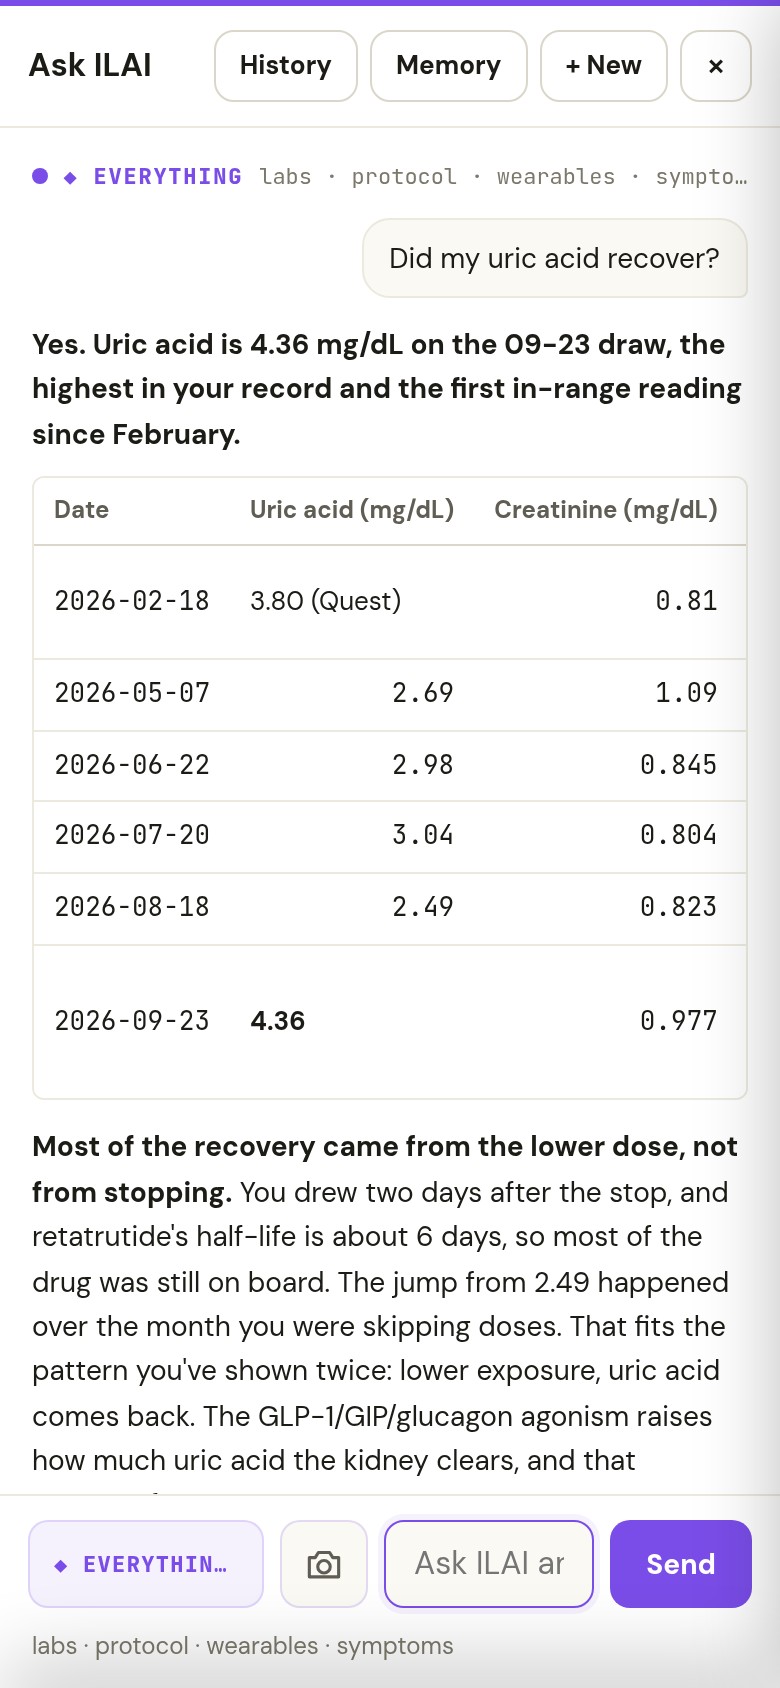
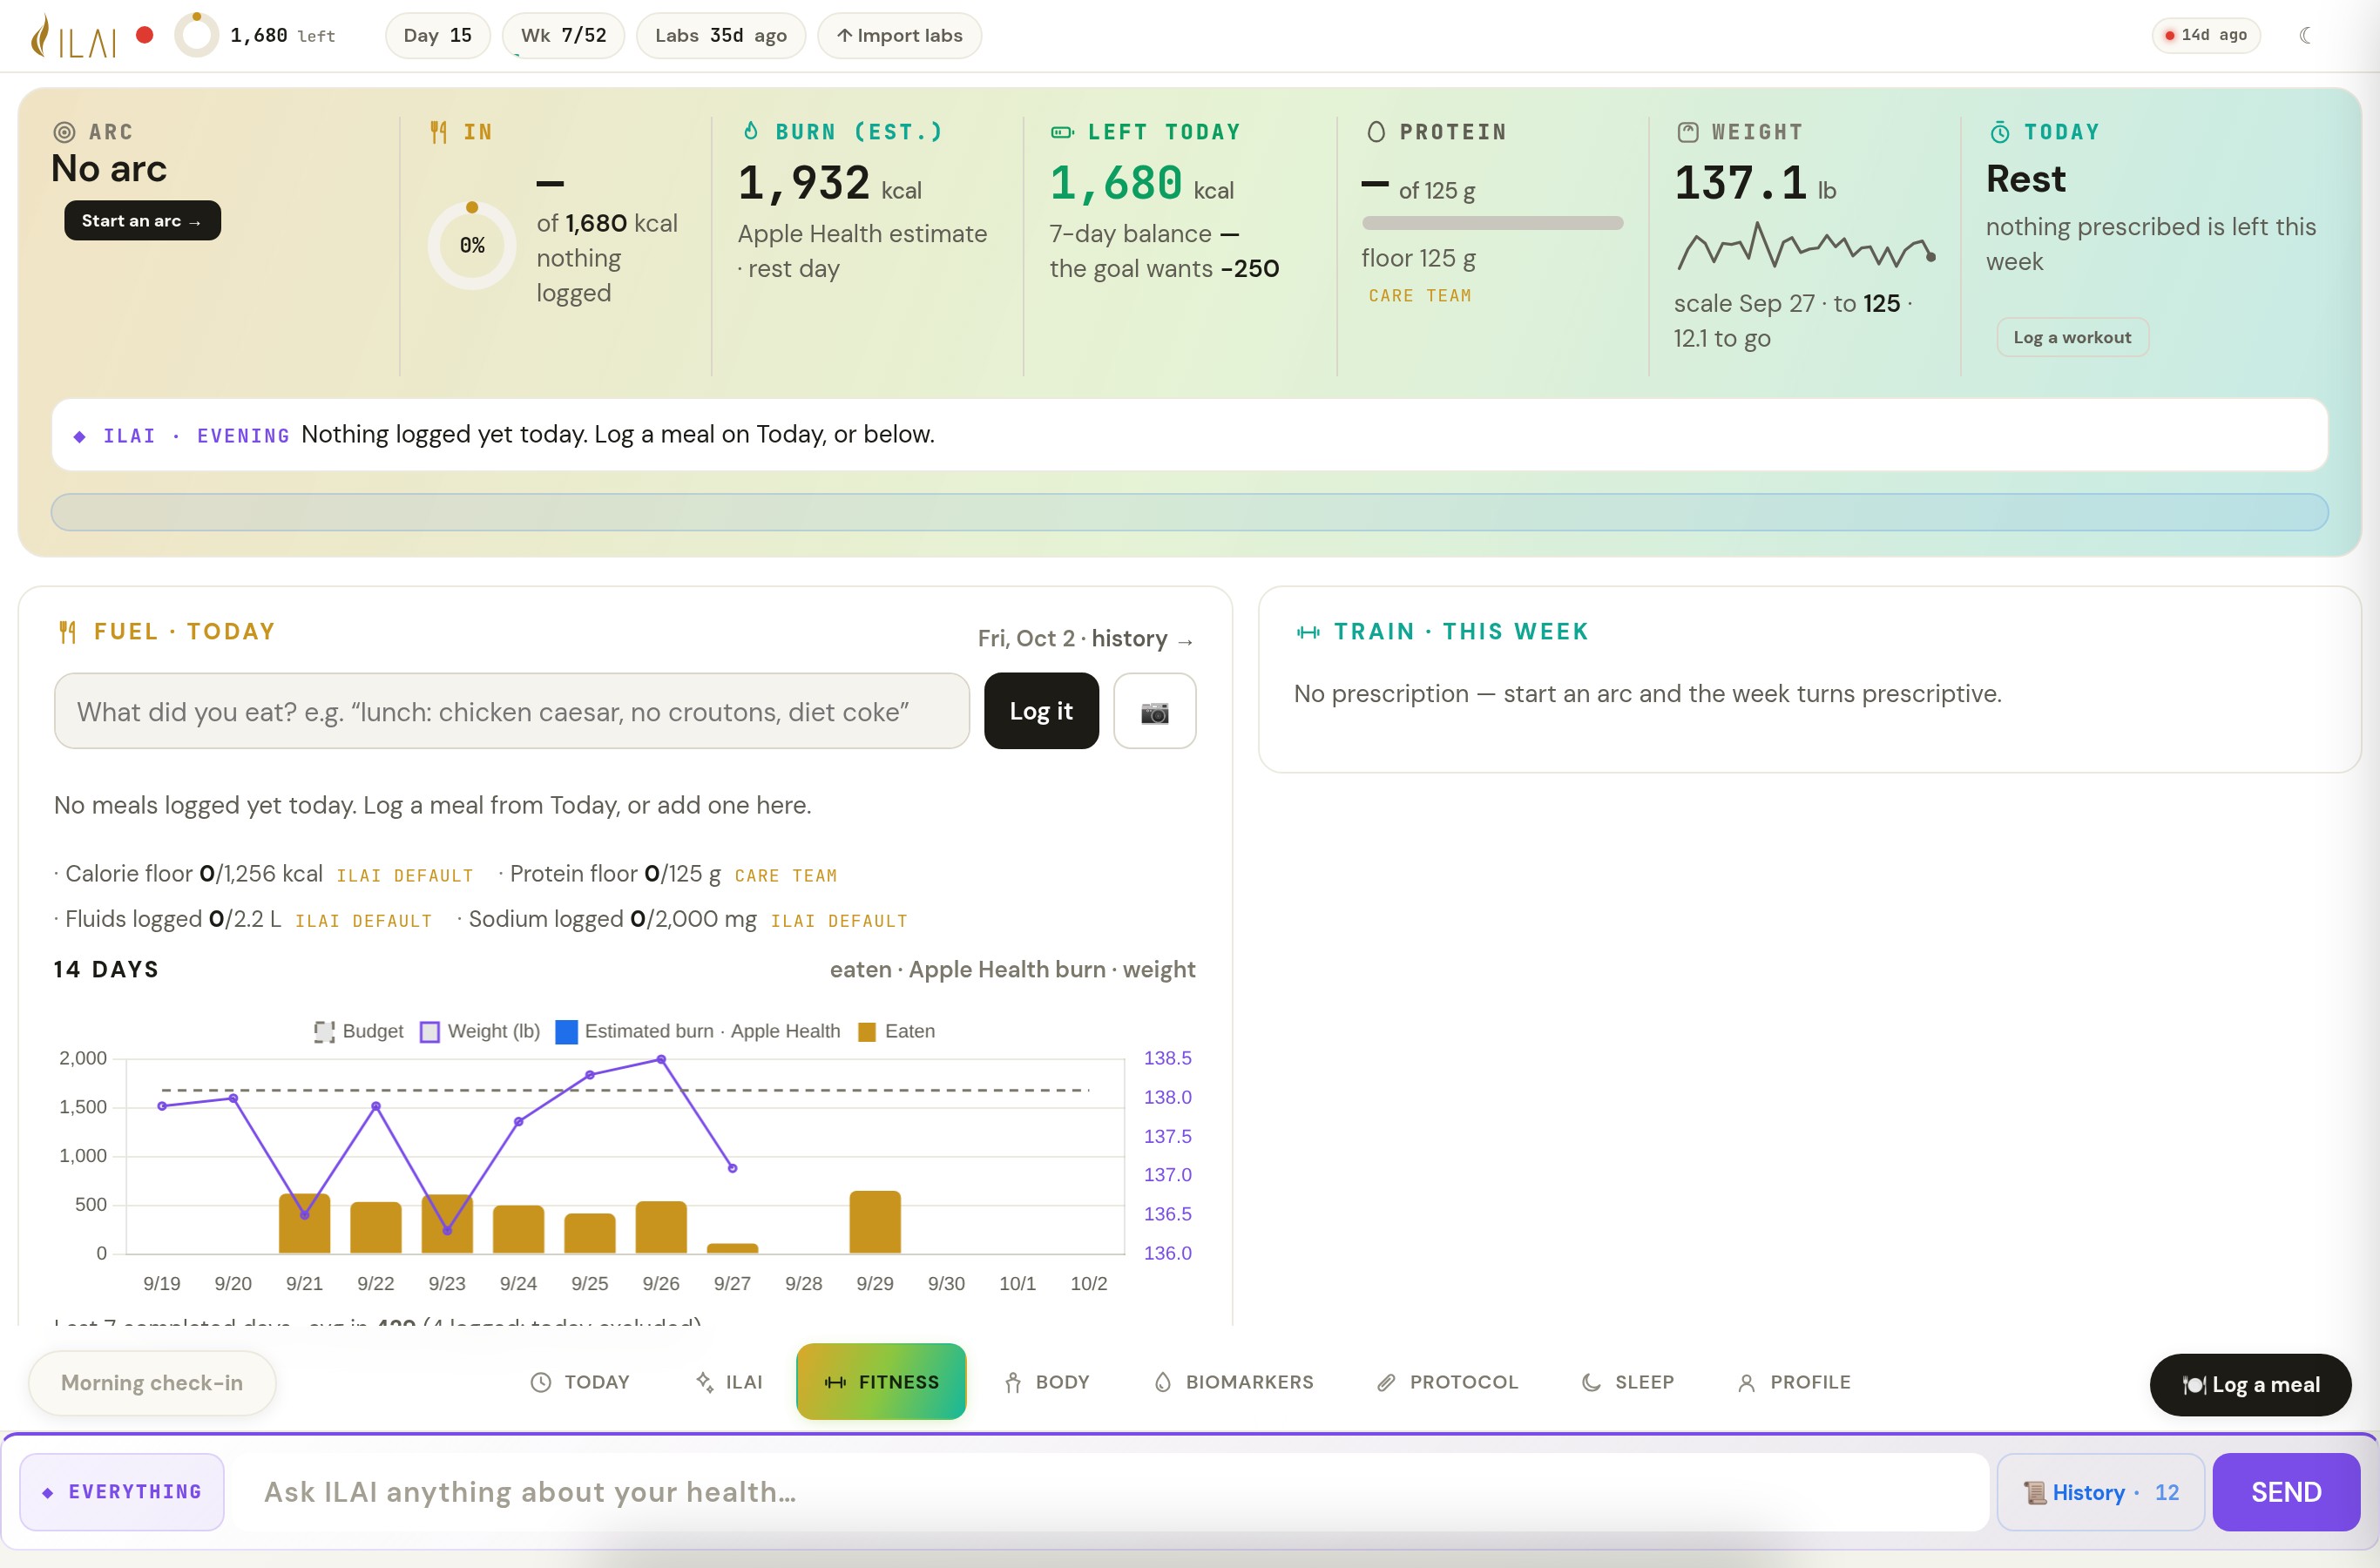
Training and sleep are read against the labs. A rising hematocrit or a low HRV changes the week’s plan.
What went in, what went out, and the session the labs allow.
- The day, readagainst the floors set for the patientinoutleft todayproteinweighttoday’s session
- An arcweeks with a purpose, following the protocolbuildcutcruiserecovertravel
- Fuel follows the arca ceiling from Apple Health energy, targets set per patientmeals by text or photoILAI at noon and evening
- Adjustments tied to the datathe value shows on the planuric acid ▼ → no intervalsHRV ▼ → lower intensityhematocrit ▲ → no VO₂ testdays under the ceiling → lower intensity
- Every session countedand kept honestfrom the watchlogged by hand when the phone was deada slow walk is an easy walk, not zone 2
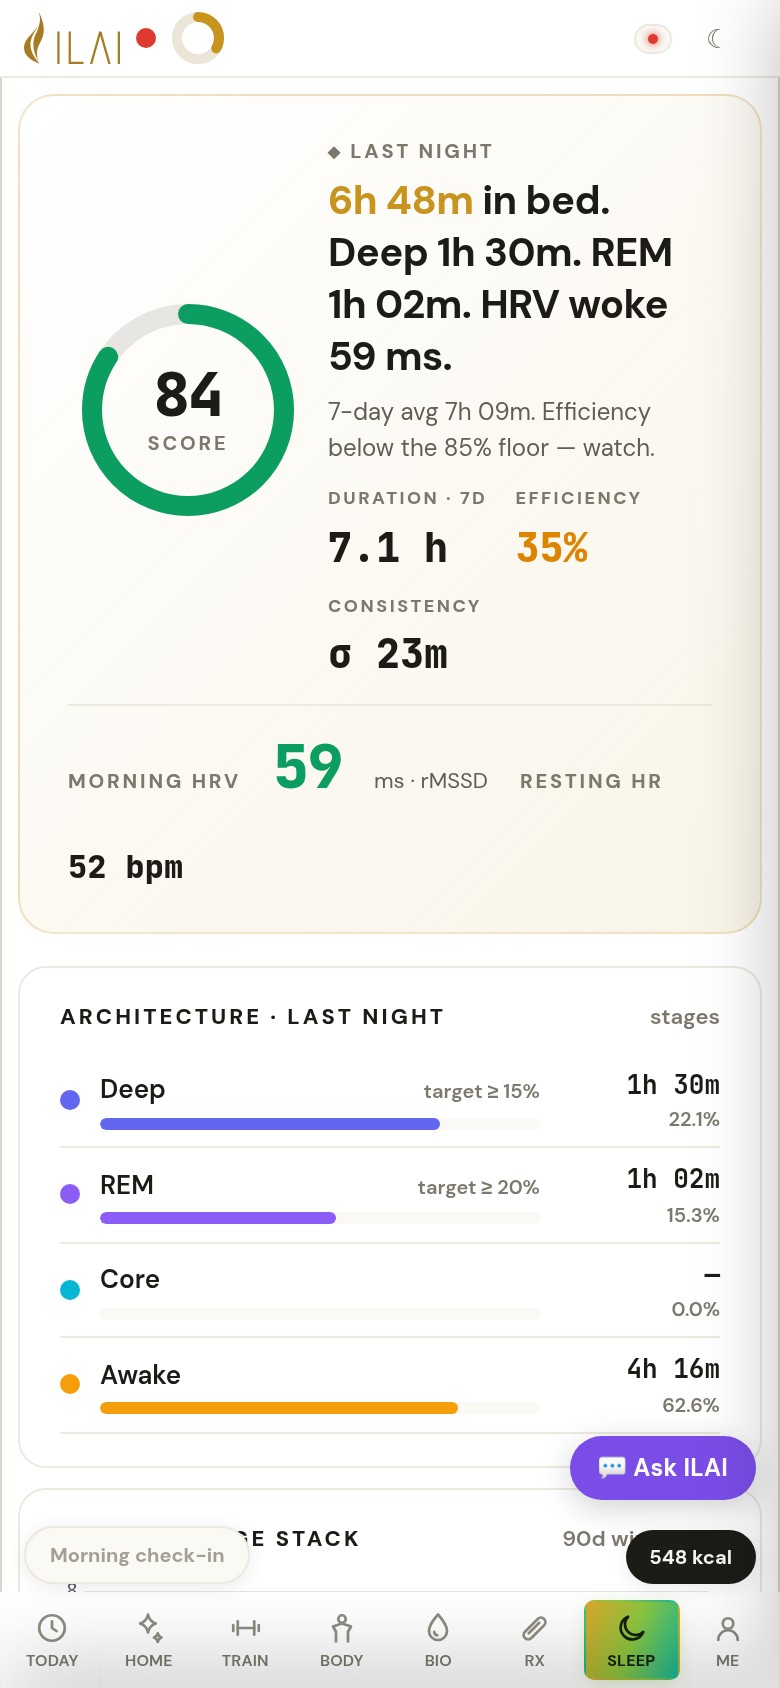
Scored, correlated, and read every morning.
- Scored nightlyagainst targetsdeepREMcoreawake
- Correlated90 days of their own nightssleep → HRVsleep → resting HRcorrelation and nights counted, shown
- Highlights a practical next stepone actionlock bedtimemore sleep for REMsleep study
Weeks with a purpose, on the way to a date.
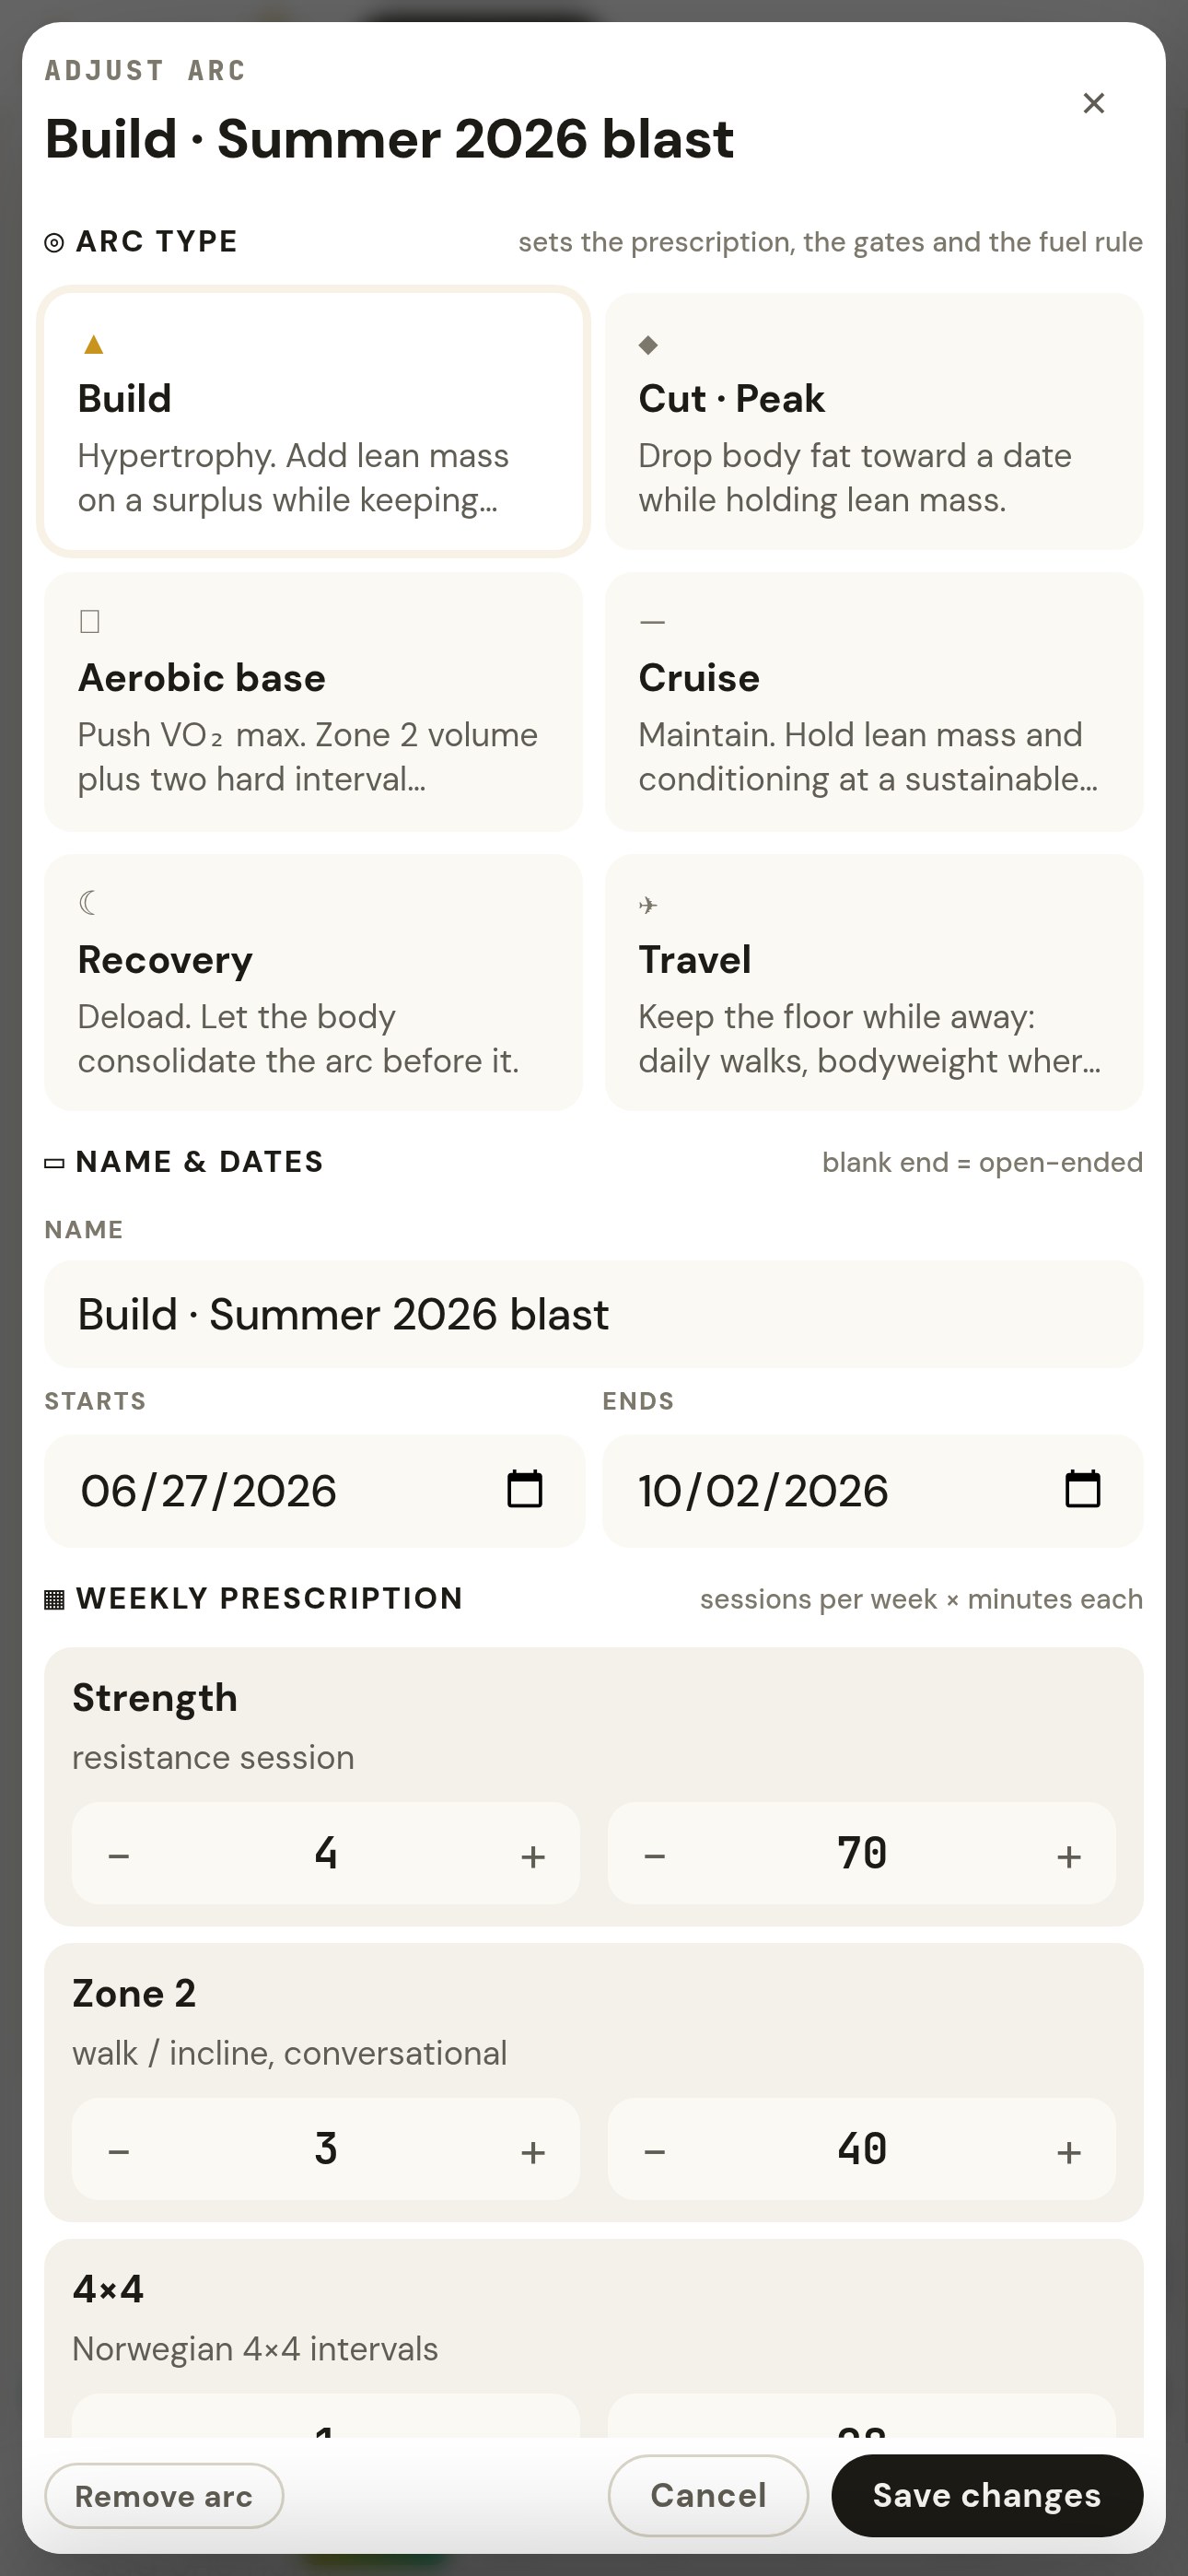
A season carries the target date. Arcs carry the work: Build, Cut · Peak, Aerobic base, Cruise, Recovery, Travel. Each sets the weekly prescription, the photo cadence, the gates from the labs and the fuel rule. Alex’s Build arc is on day 93 of 98: resting heart rate down 10 and HRV down 4.6 since it began, sessions at 25% of prescription.
- The prescription, editable per arcsessions per week and minutes each, plus a daily step floor
- Gates from the labs and recoveryuric acid, HRV, hematocrit and fuel each block or downgrade a session type
- Photo check-ins on the arc’s cadencewith an ILAI visual read against the scale
- Since the arc beganweight, body fat, lean mass, resting HR and HRV against the start
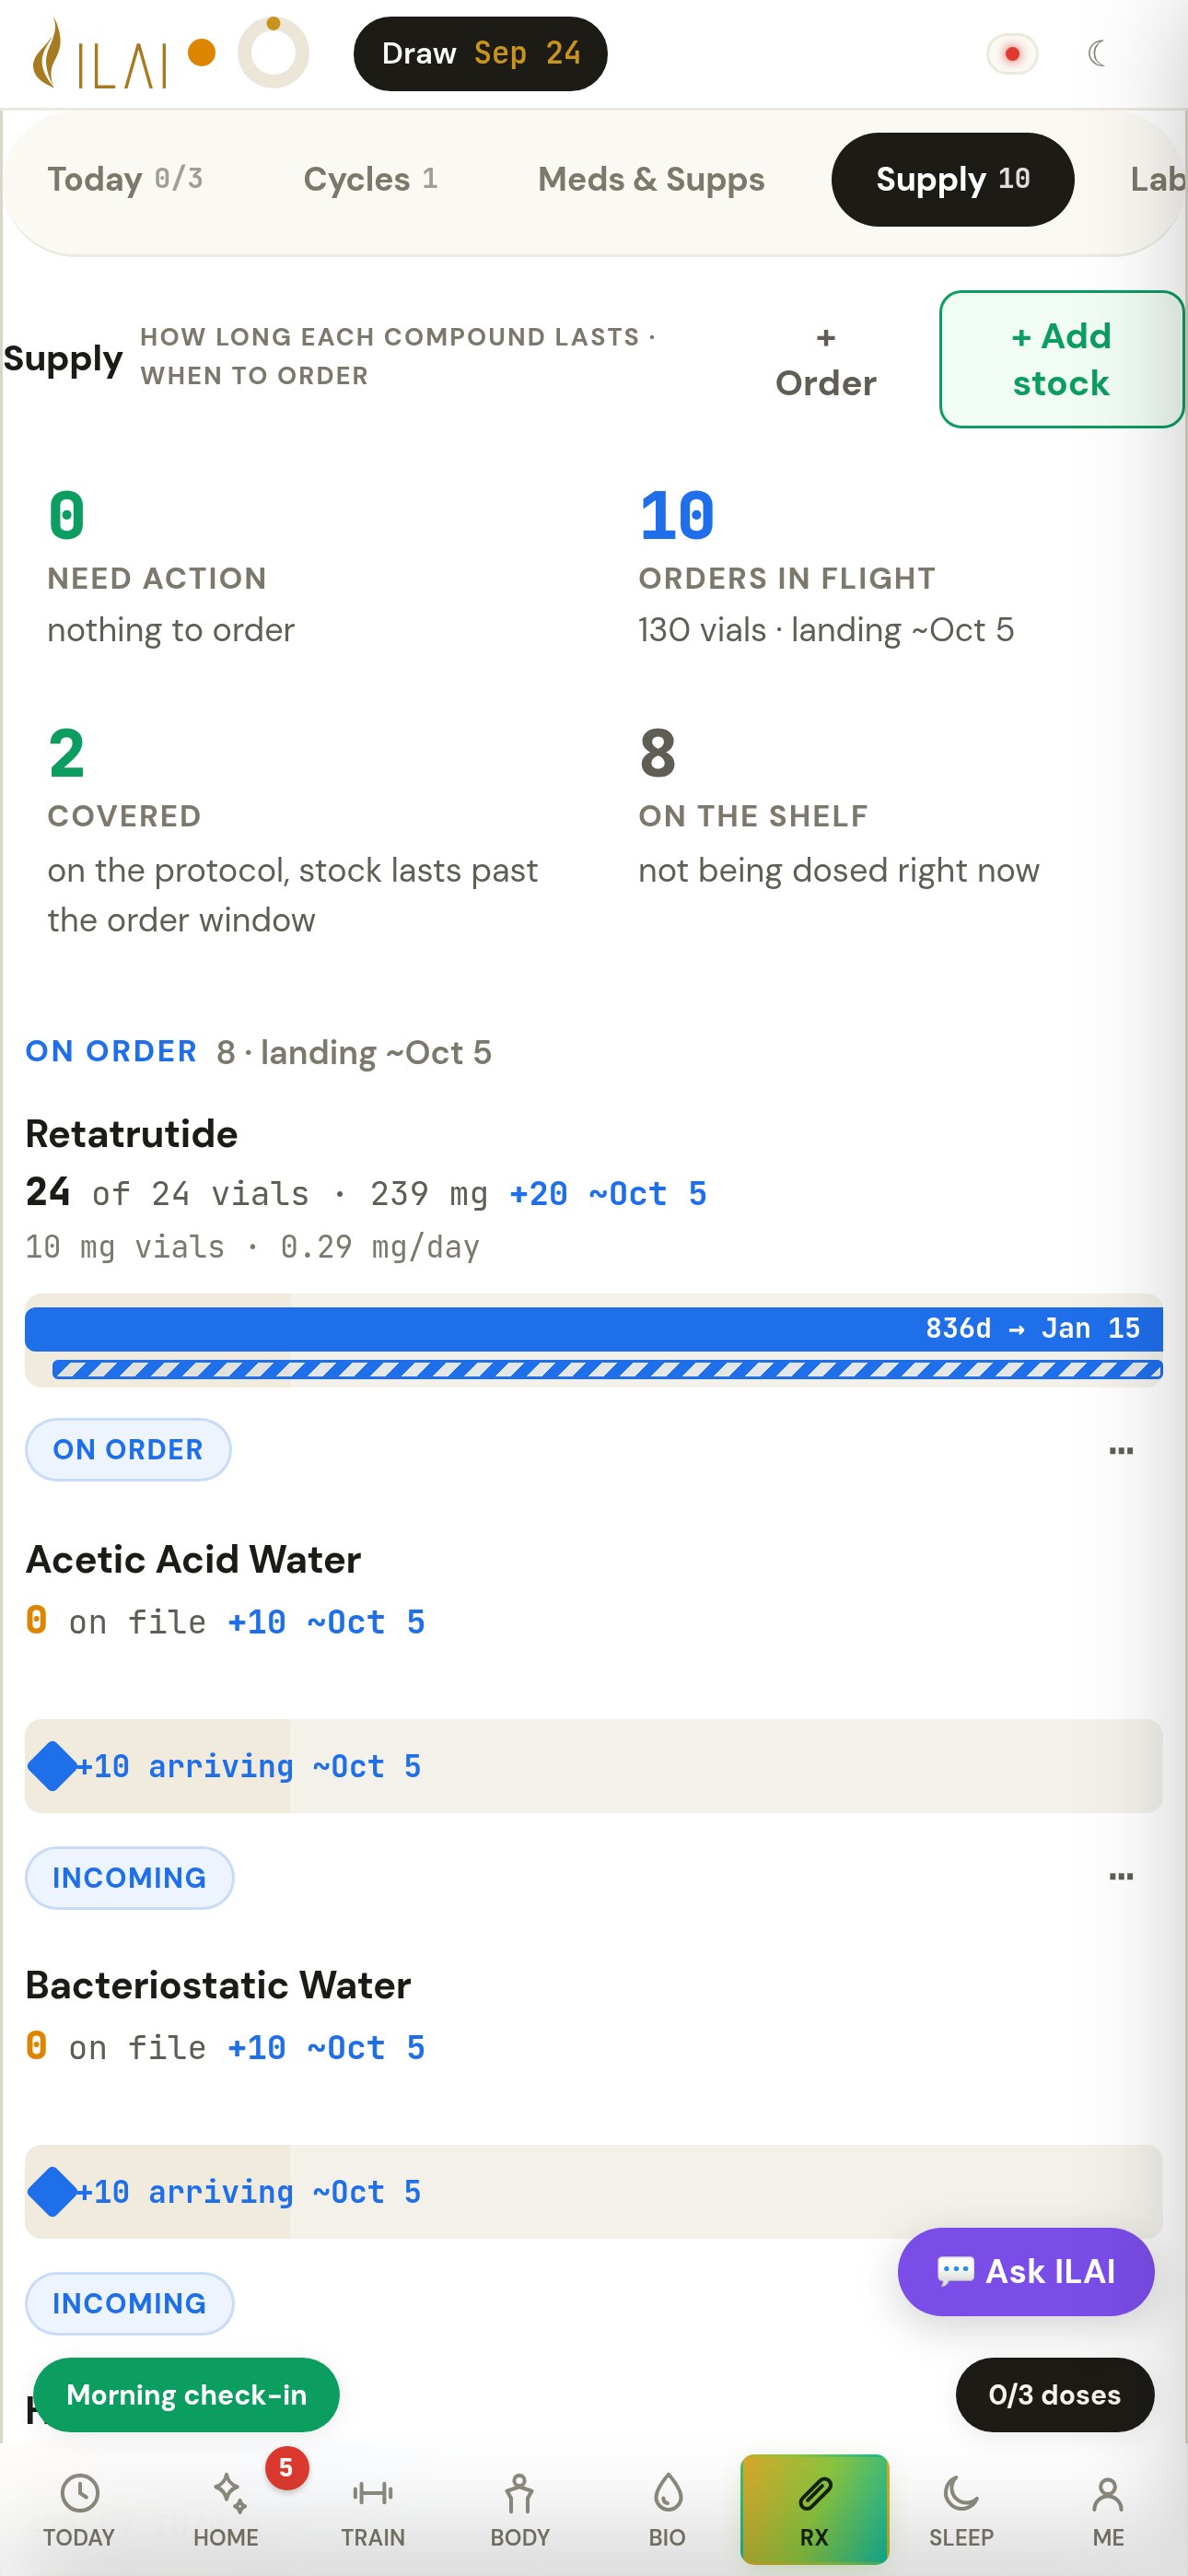
How long each compound lasts. When to order.
Supply reads every lot against the dose: what is on hand, what is on order, when it runs dry, and the order window ahead of a 28-day lead. Refill requests carry their status. Monday’s report and the clinician’s Needs-you list carry the practice’s week, findings first.
- Lots and vial lifeon hand against the daily dose, with the day it runs dry
- Orders in flightlanding dates on the timeline, incoming stock marked
- Refill requests with statusrequested, sent, delivered or cancelled, per compound
- The Monday reportevery patient’s week by email, findings first
See it for your patients.
Thirty minutes on synthetic patients, then what setup would look like in your practice.
Not with a practice? ILAI for iPhone is coming to the App Store; join the list.